Tag: optimum infinite

Refitting Success: Reducing Suction and Maximizing Oxygen Permeability

[us_post_title][us_post_date][us_separator size=”small”]

By Karen Carrasquillo, OD, PhD, FAAO, FSLS, FBCLA

Case Summary

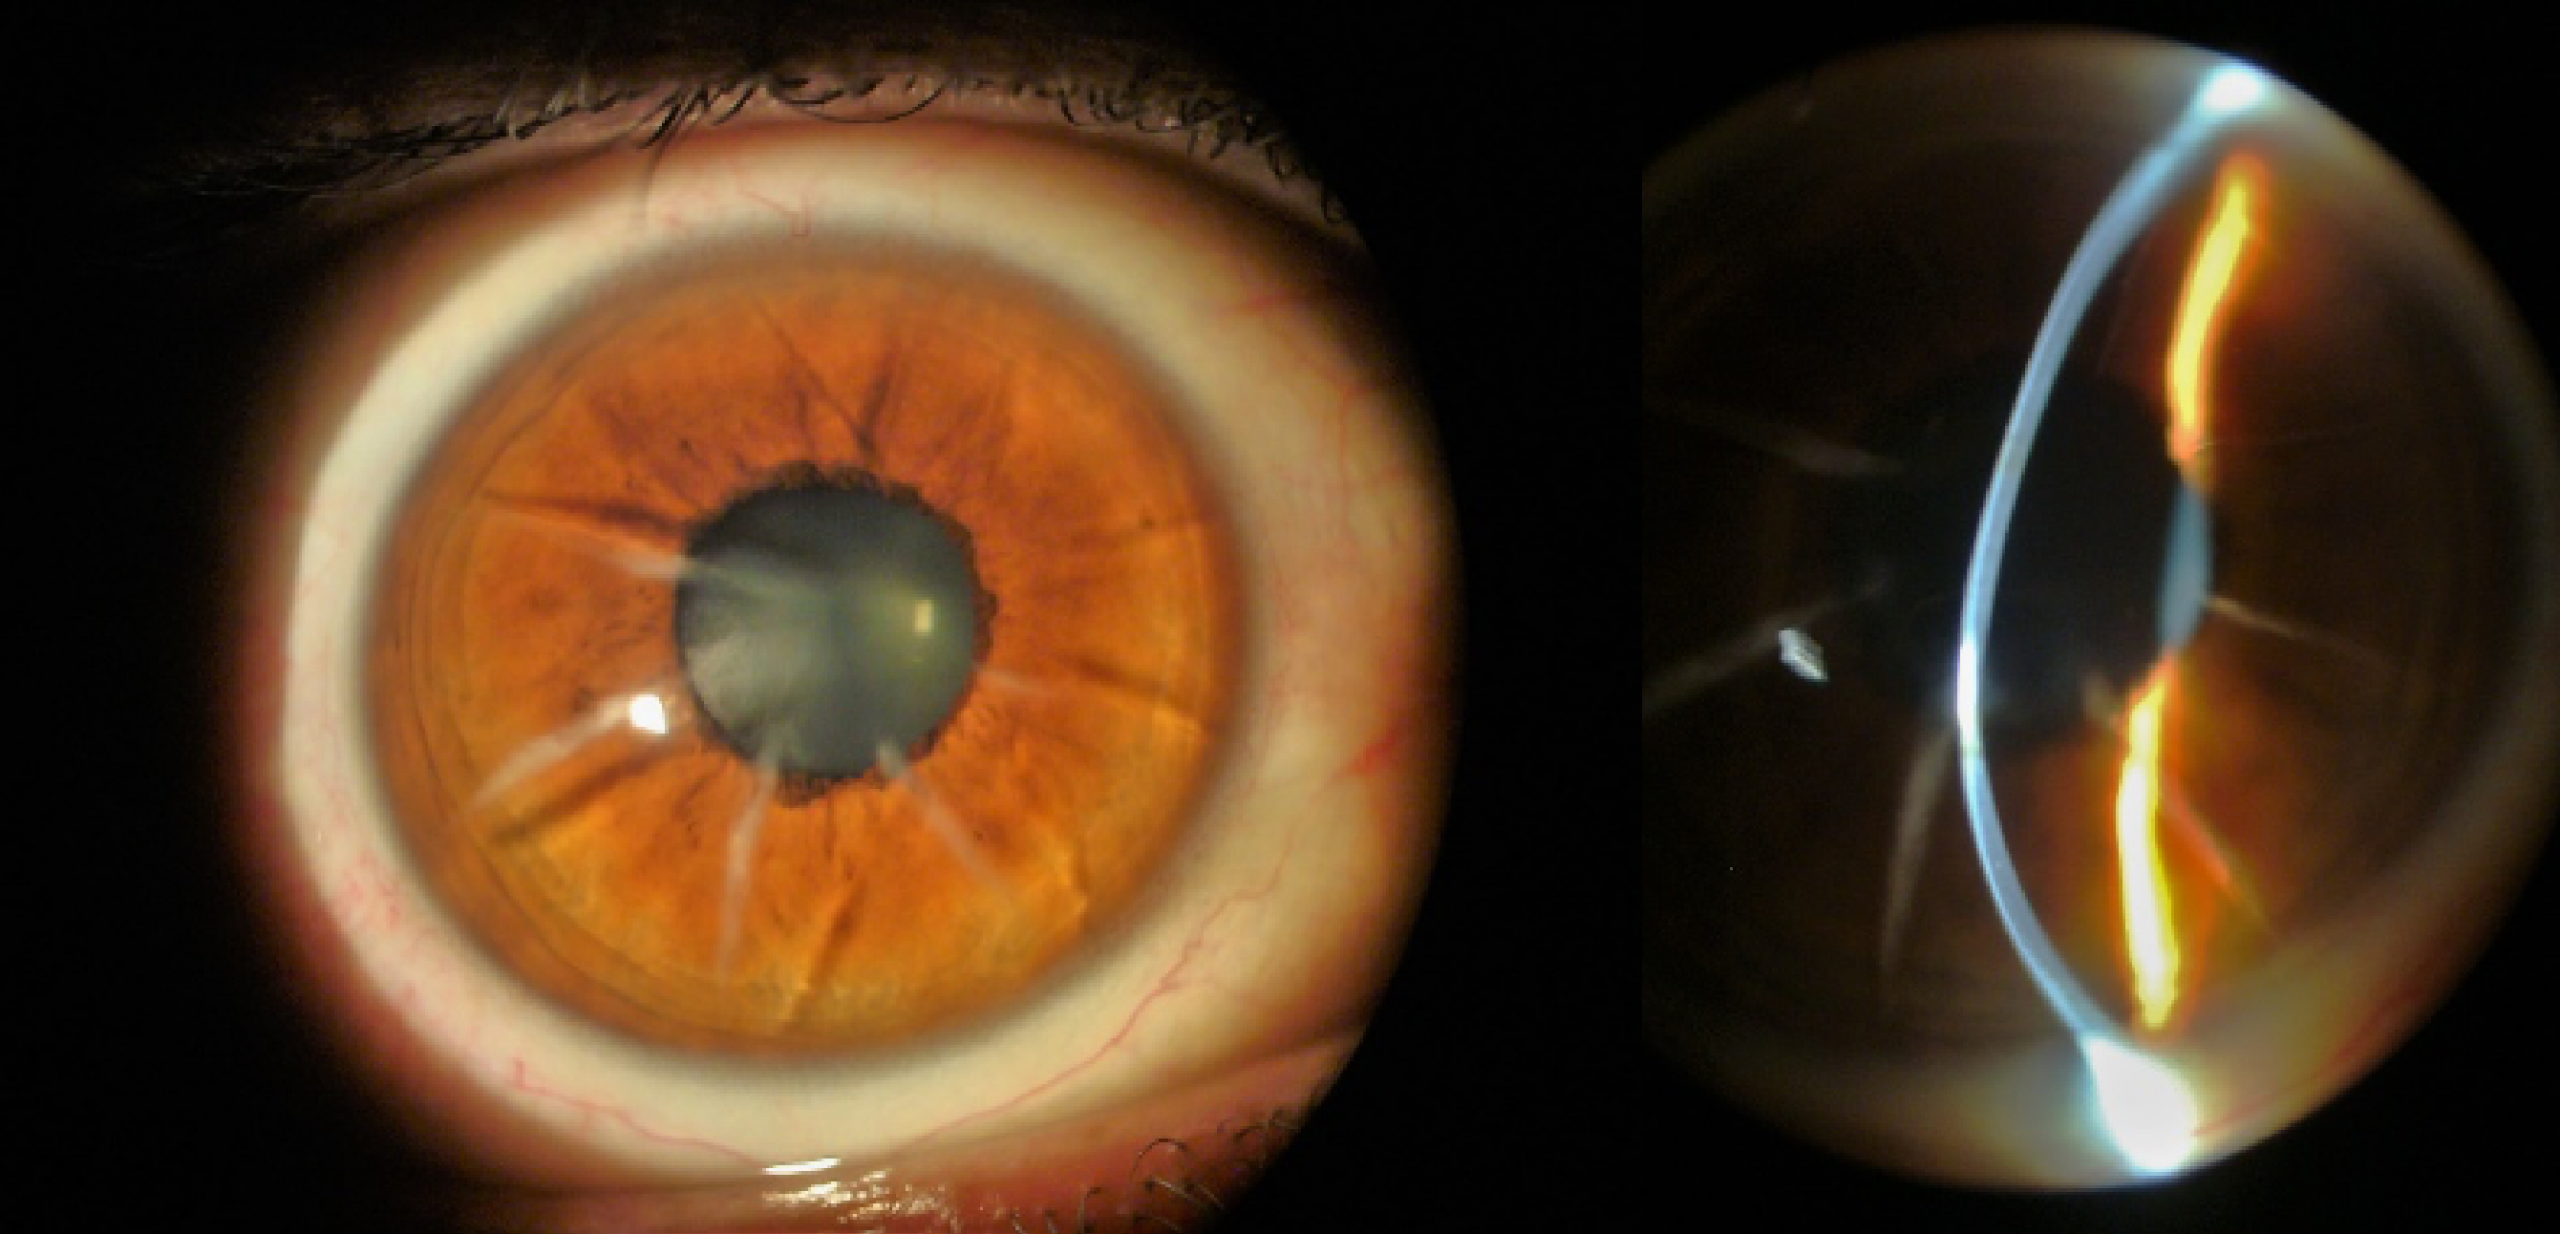
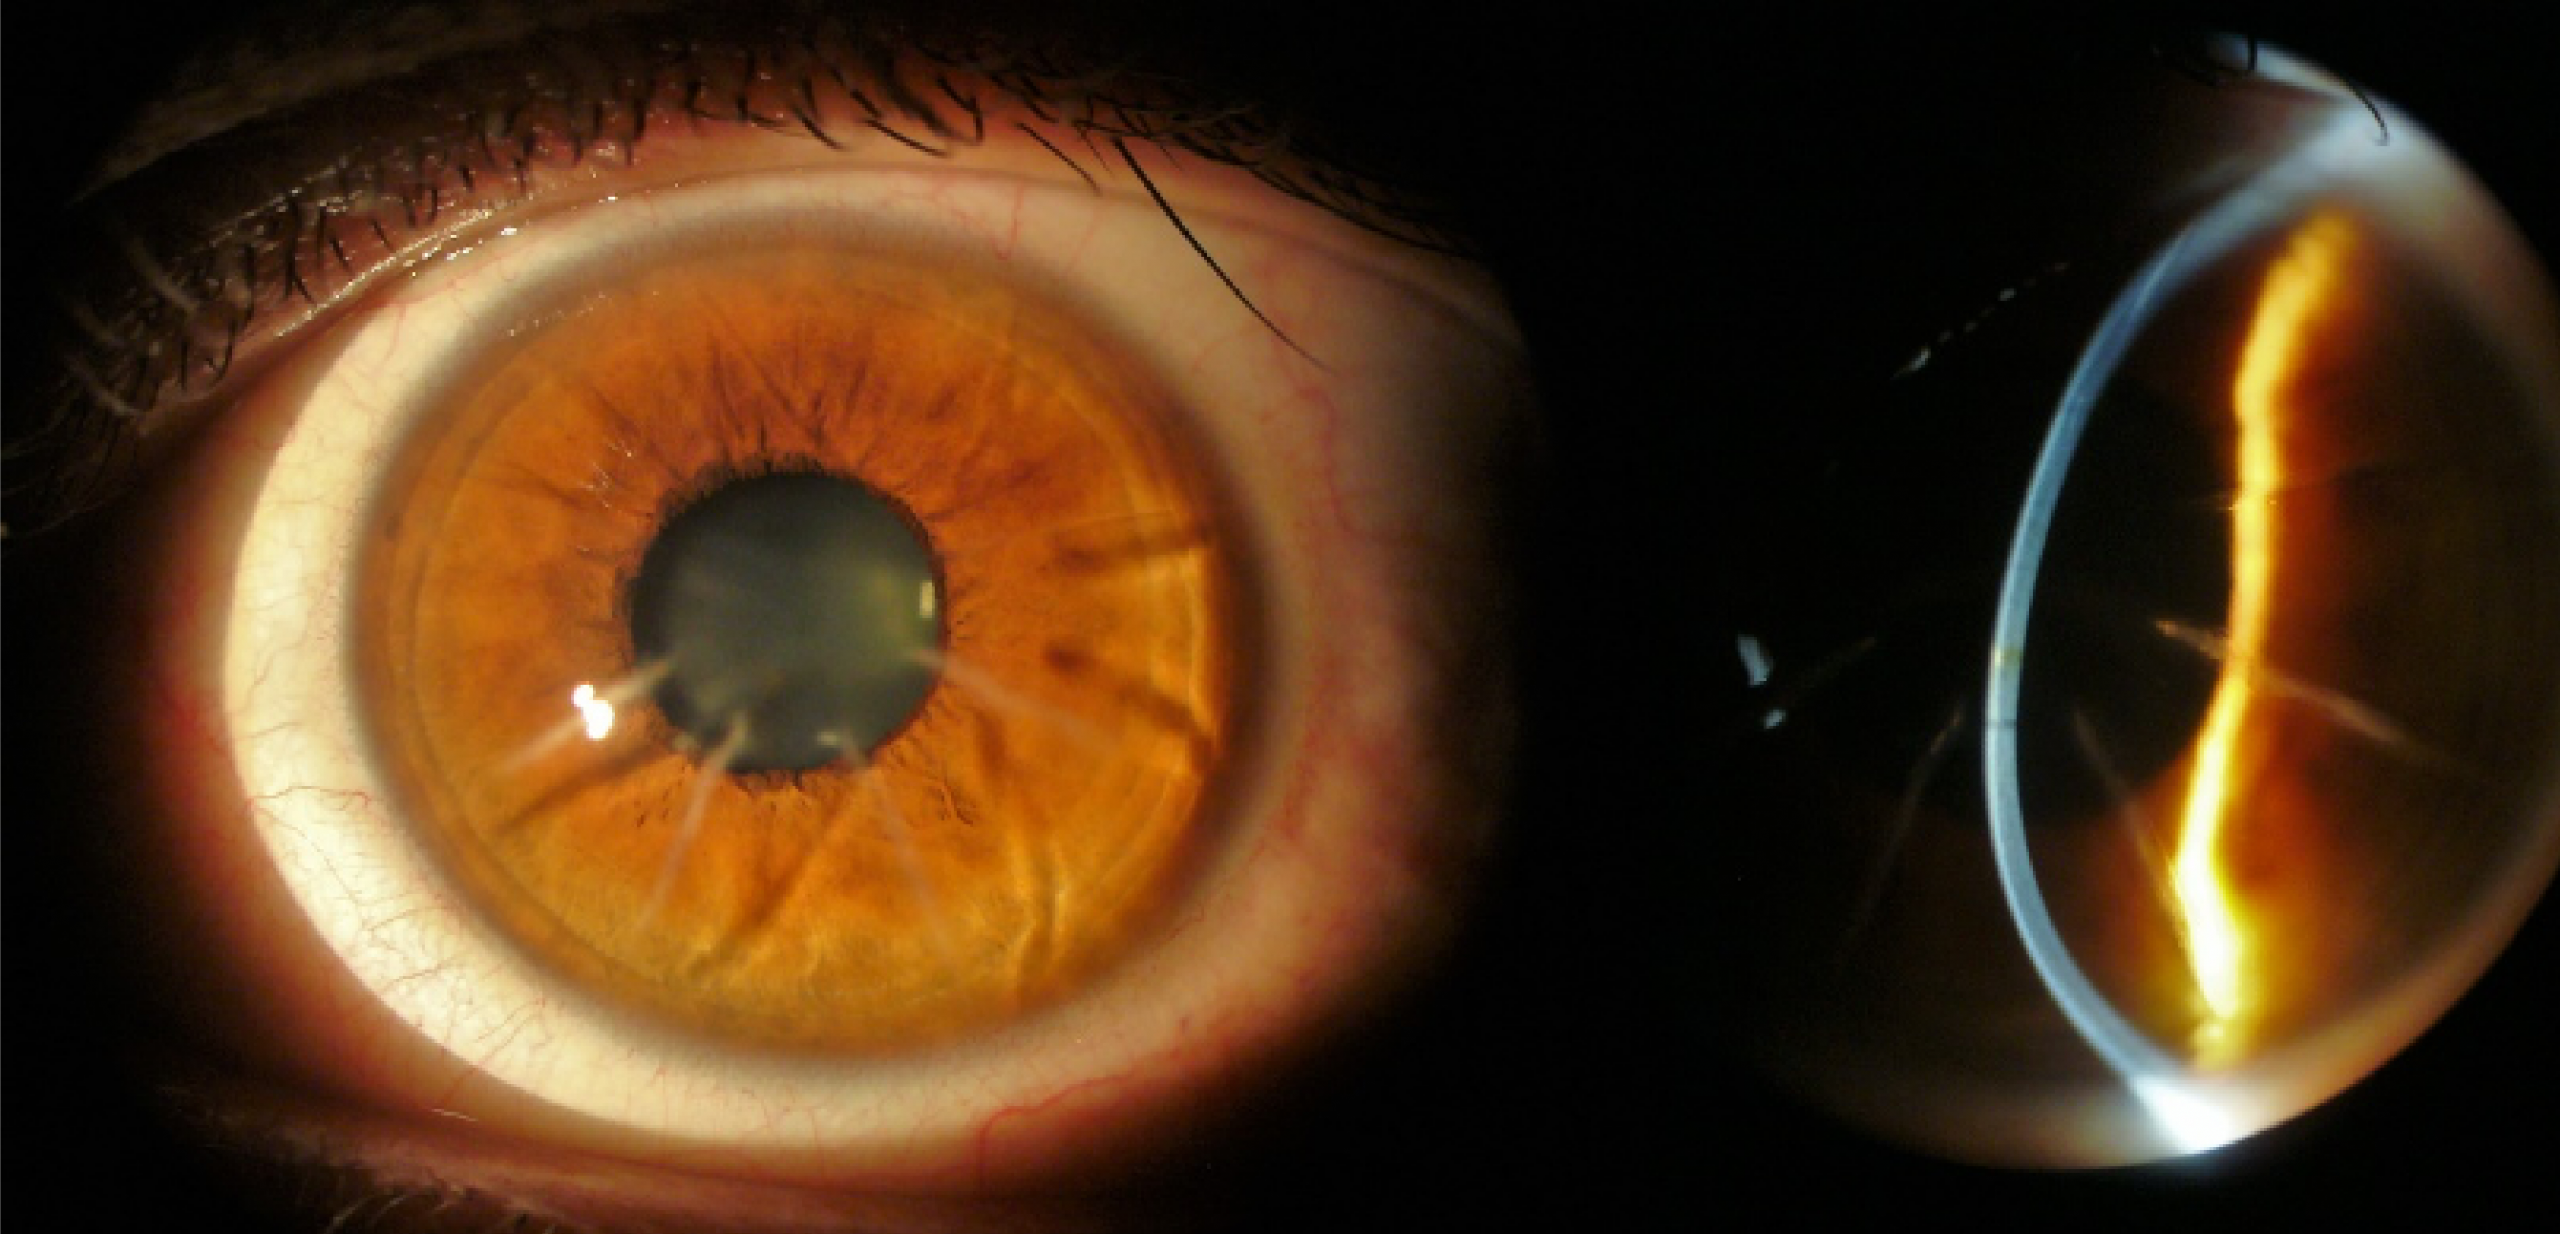
Case of a 60-year-old woman with a history of keratoconus and dry eye syndrome in both eyes, history of corneal scraping in the left eye 25 years prior, history of post hydrops left eye, and questionable potential history of amblyopia left eye. She had a history of successful PROSE treatment since 2010 (11 years of PROSE device wear) but underwent penetrating keratoplasty (PKP) in the left eye in December 2019; secondary to diffuse opacification (Figure 1) and limited best corrected visual acuity.

Prior to PKP in the left eye, she had been wearing 18.5mm, quadrant-specific PROSE devices in both eyes, with added front-surface astigmatism in the right eye and with resultant best corrected visual acuity (BCVA) of 20/30, PH 20/25-2 and 20/100, PH 20/60–, right eye and left eye respectively. With prescribed polycarbonate spectacles to correct residual astigmatism in the left eye and to serve as protection (especially for the better-seeing eye), BCVA in the left eye could be improved to 20/70. The patient wore the spectacles as needed, depending on daily activities and especially during night driving.
Reducing Suction and Maximizing Oxygen Permeability

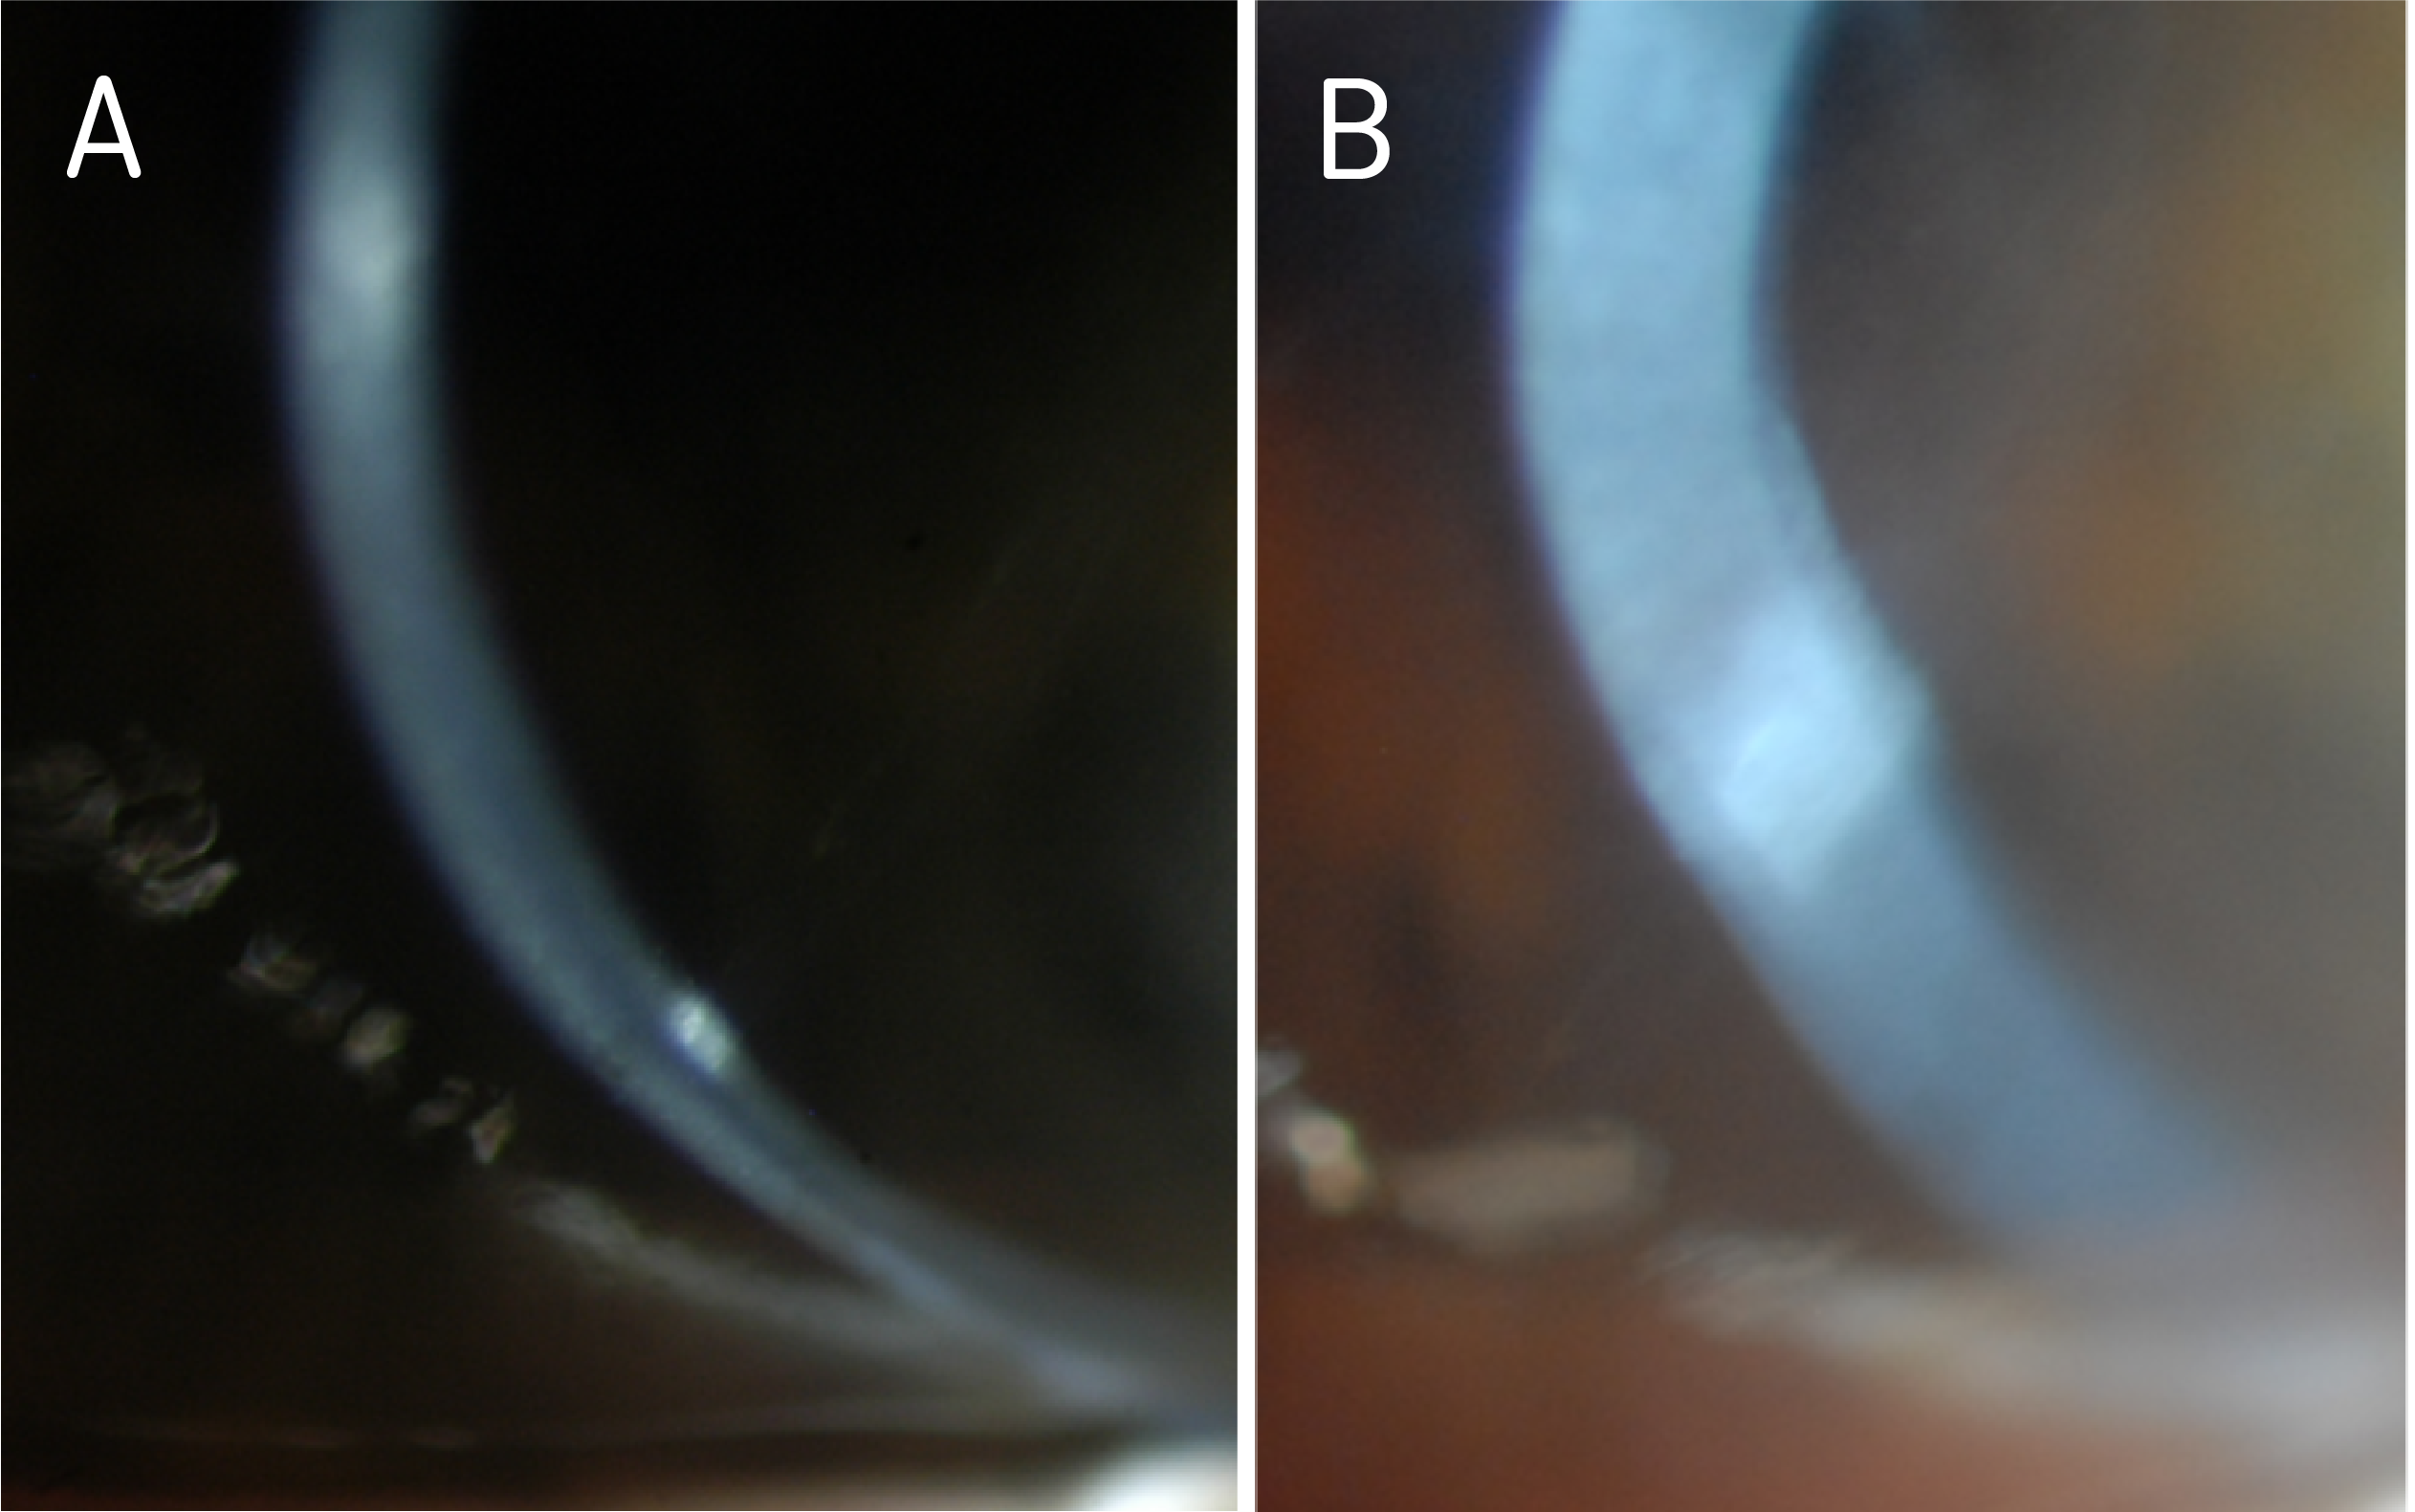
Figure 1. Diffuse haze and opacification in the left eye, as seen on optic section (A) and wide beam (B), prior to PKP.

After corneal transplantation and having been cleared to resume scleral device wear in the left eye, she was referred to our clinic for refitting.

Evaluation After Penetrating Keratoplasty

Initial evaluation after PKP OS (Topography shown in Figure 2A), showed a clear and compact graft, with interrupted sutures (Figure 2B). There was no evidence of subepithelial infiltrates, microcystic edema, no keratic precipitates, or stromal diffusion after corneal staining. The patient was on Prednisolone acetate 1% gtts QD and as sutures were removed, she was prescribed Moxifloxacin 0.5% TID in the left eye. Evaluation was also remarkable for cataracts in both eyes, not visually significant at the moment. Best corrected vision during this visit in the right eye was 20/40, PH 20/30-2 and uncorrected visual acuity in the left eye was CF at 3’, PH 20/200.
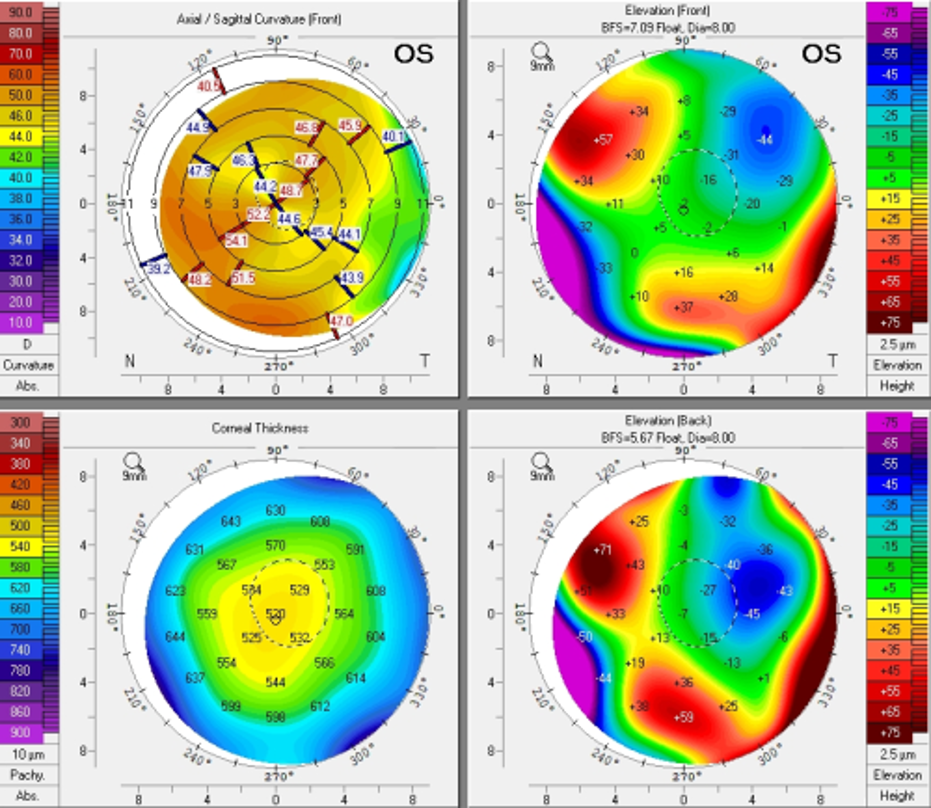
Figure 2A. Pentacam images s/p PKP in the left eye.
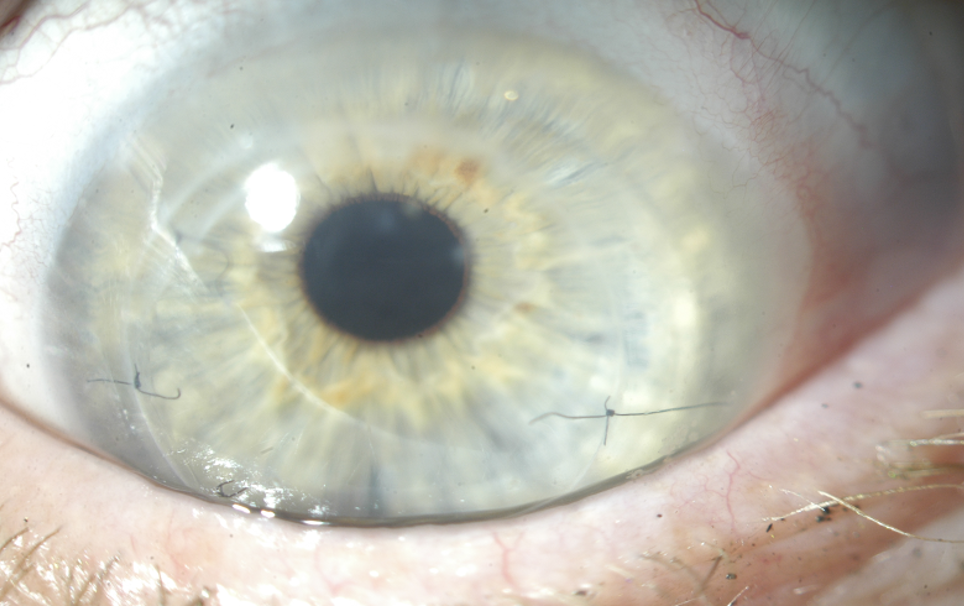
Figure 2B. Presentation of left cornea, status post corneal graft during baseline evaluation for refitting.

Refitting

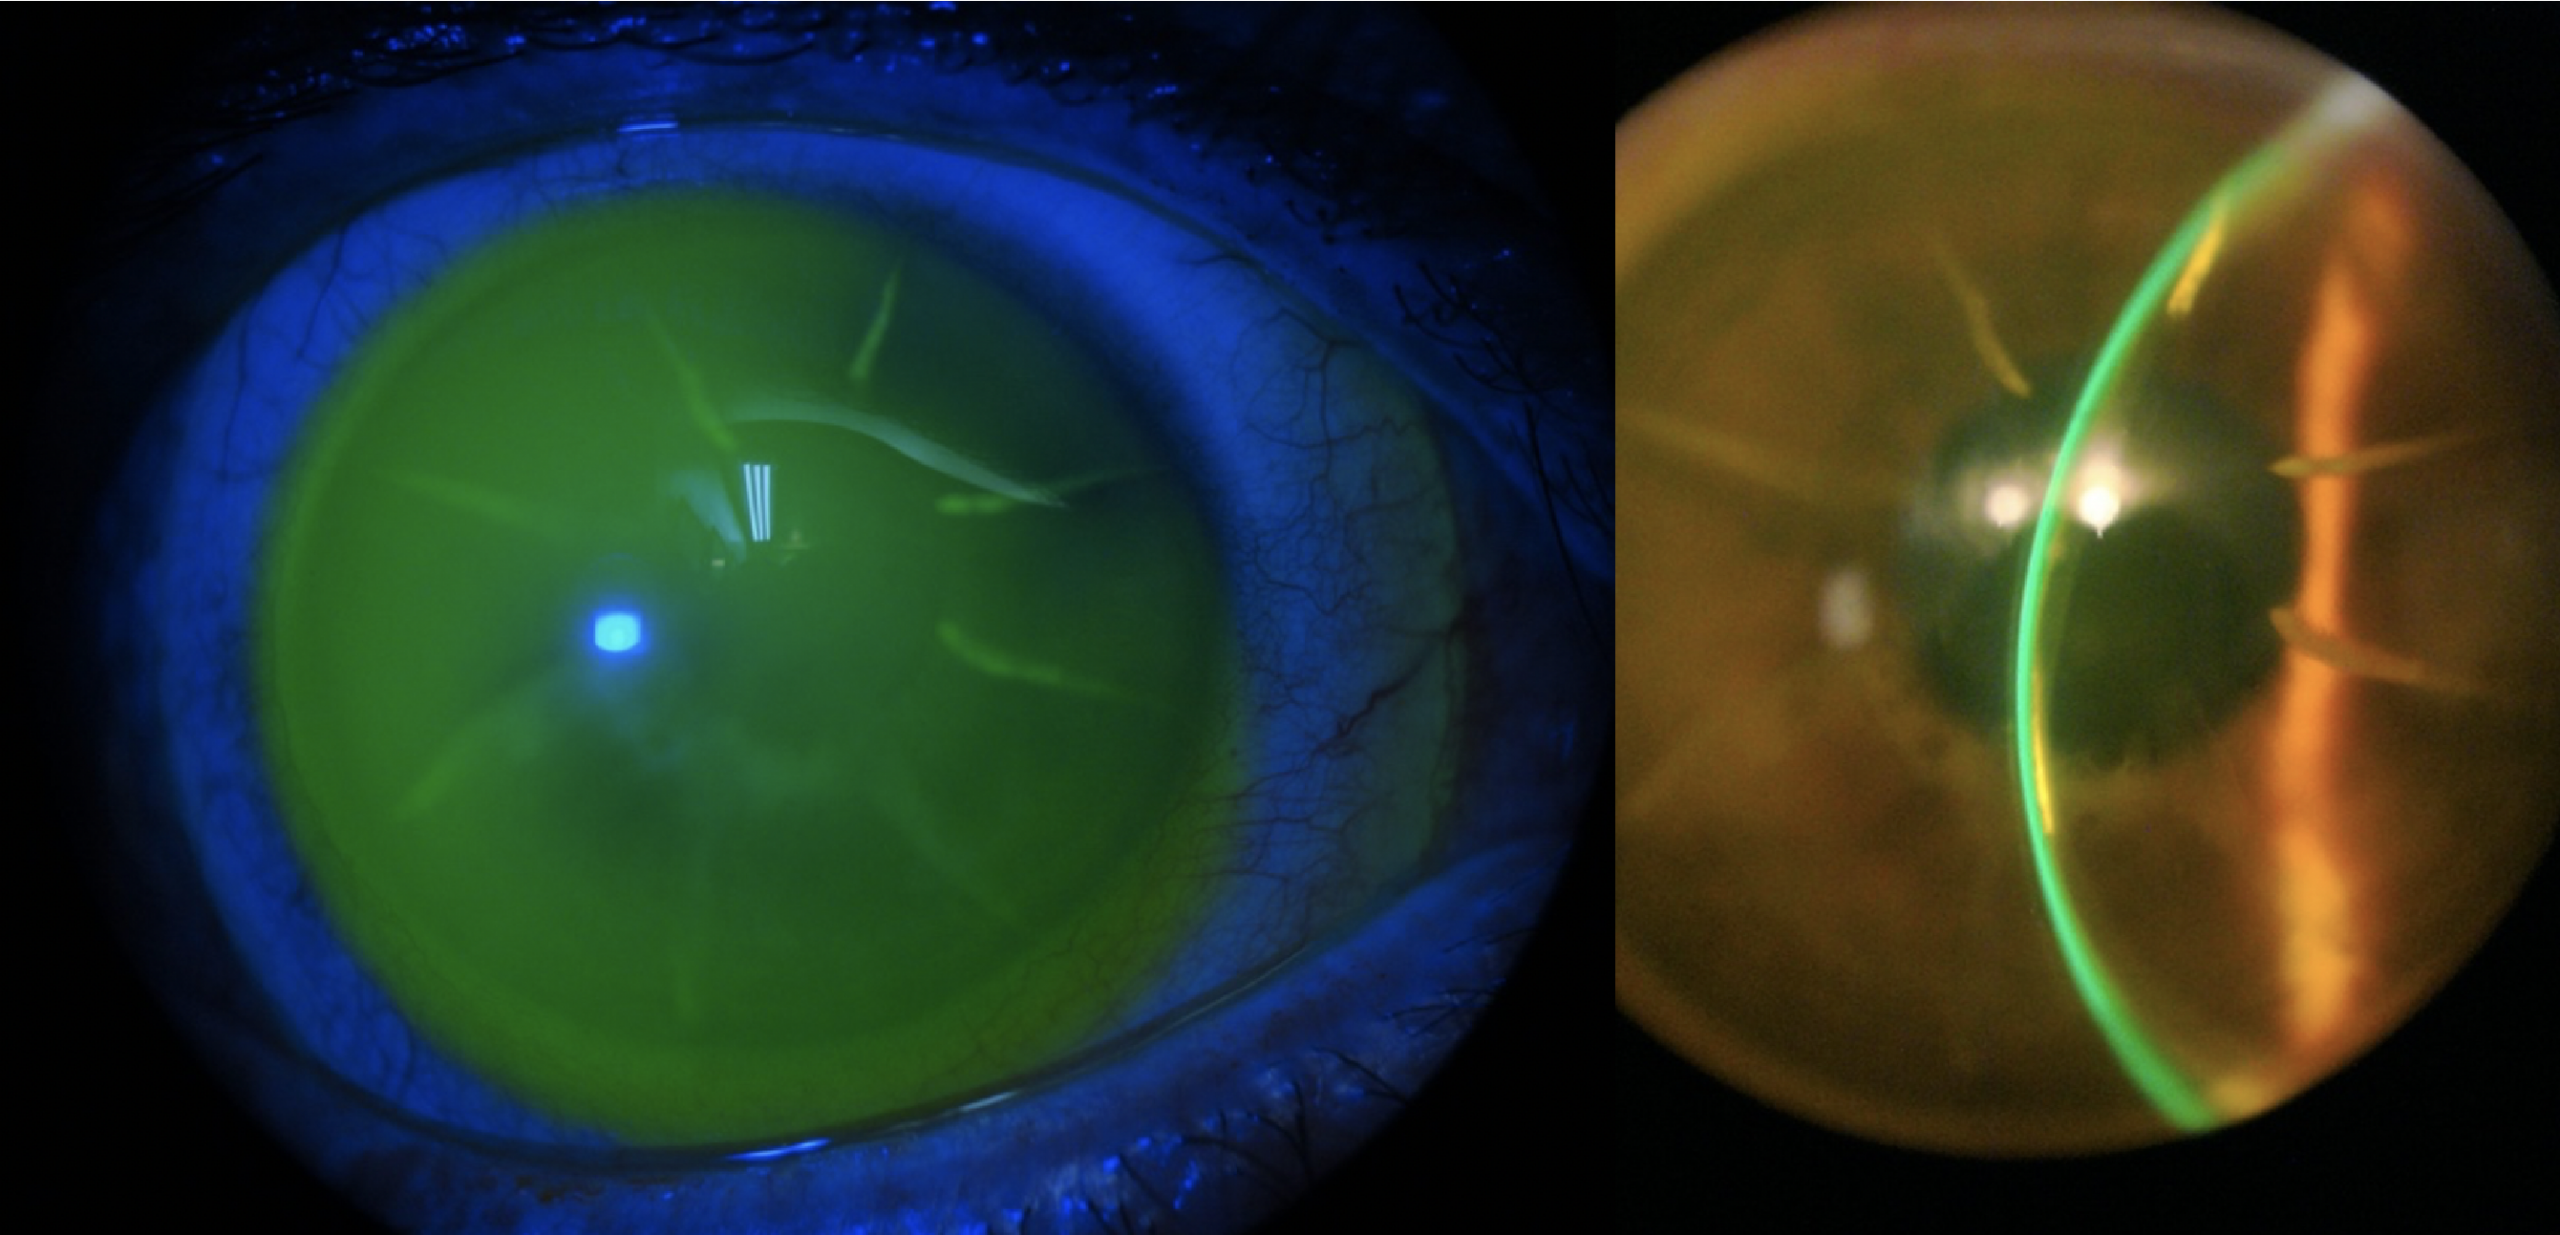
We started a new fit, deciding to keep the patient in the habitual diameter of 18.5mm. Because the cornea was now grafted, we opted to design the lens using Optimum Infinite material (180 Dk) so that together with a center thickness of 0.25mm, oxygen permeability was maximized. Best documented corrected visual acuity in the left eye was 20/30-2 with the new 18.5mm device. While the patient was elated about the newfound visual potential, she reported sensation of pressure during device wear in the left eye – despite no objective evidence of significant compression at the haptics (Figure 3).
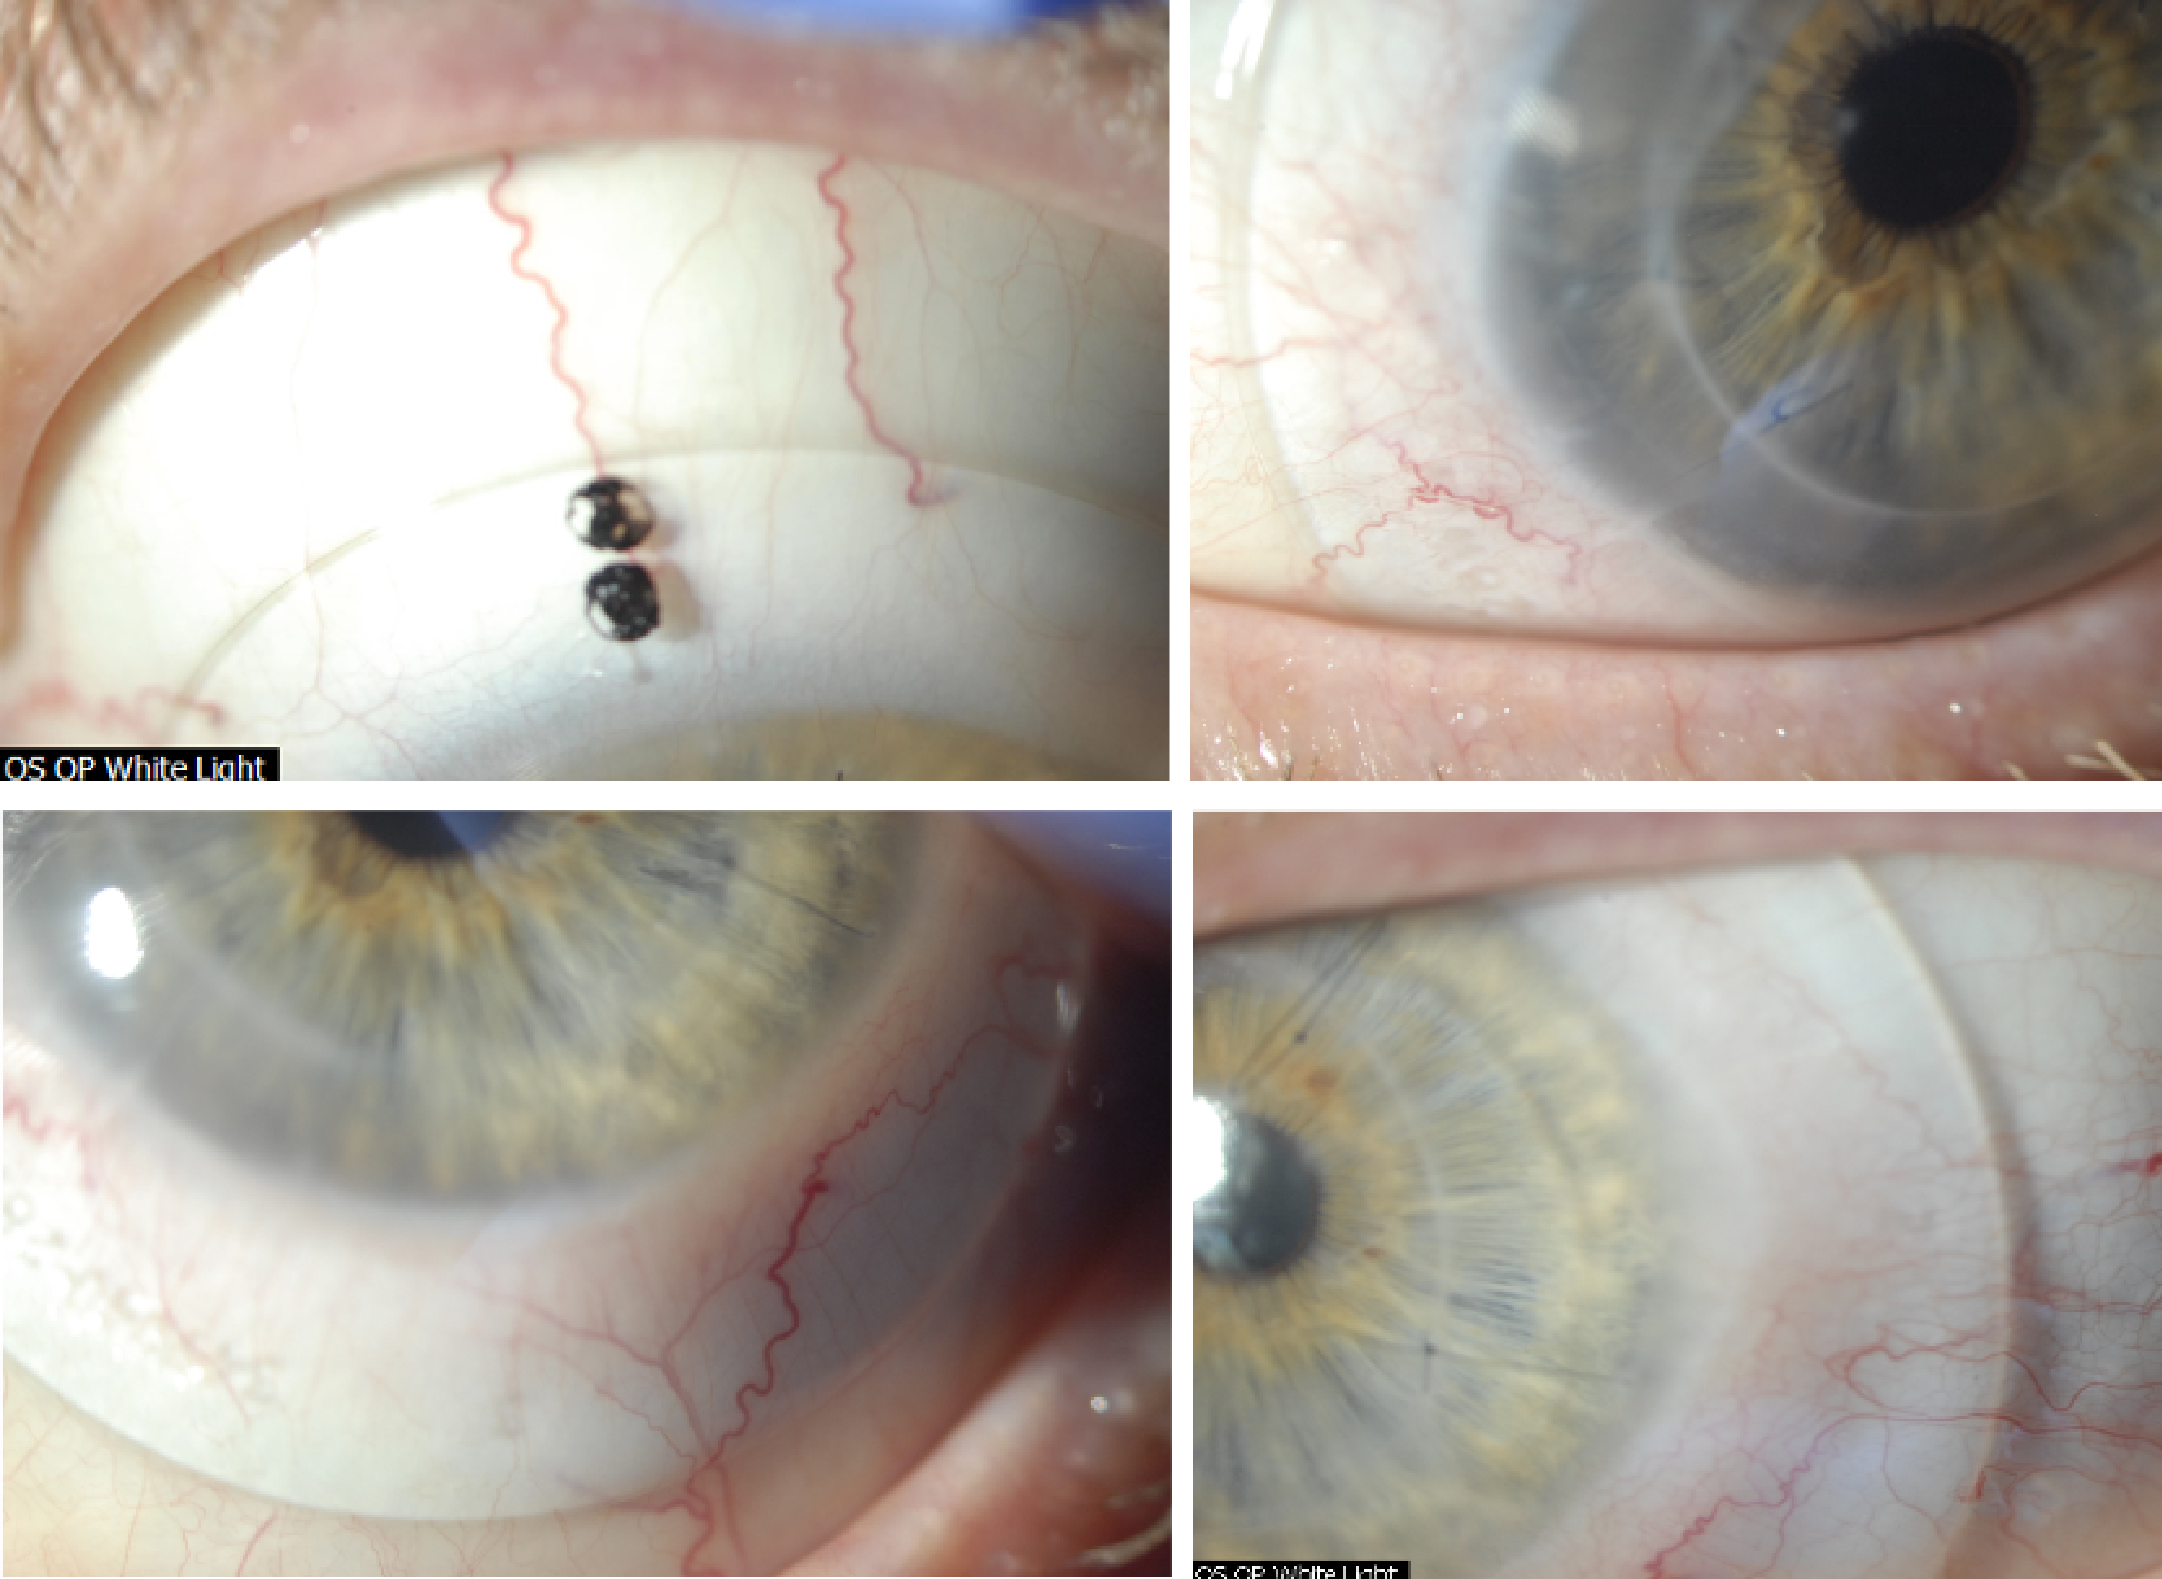
Figure 3. Initial fitting endpoint with an 18.5mm PROSE device after PKP OS.

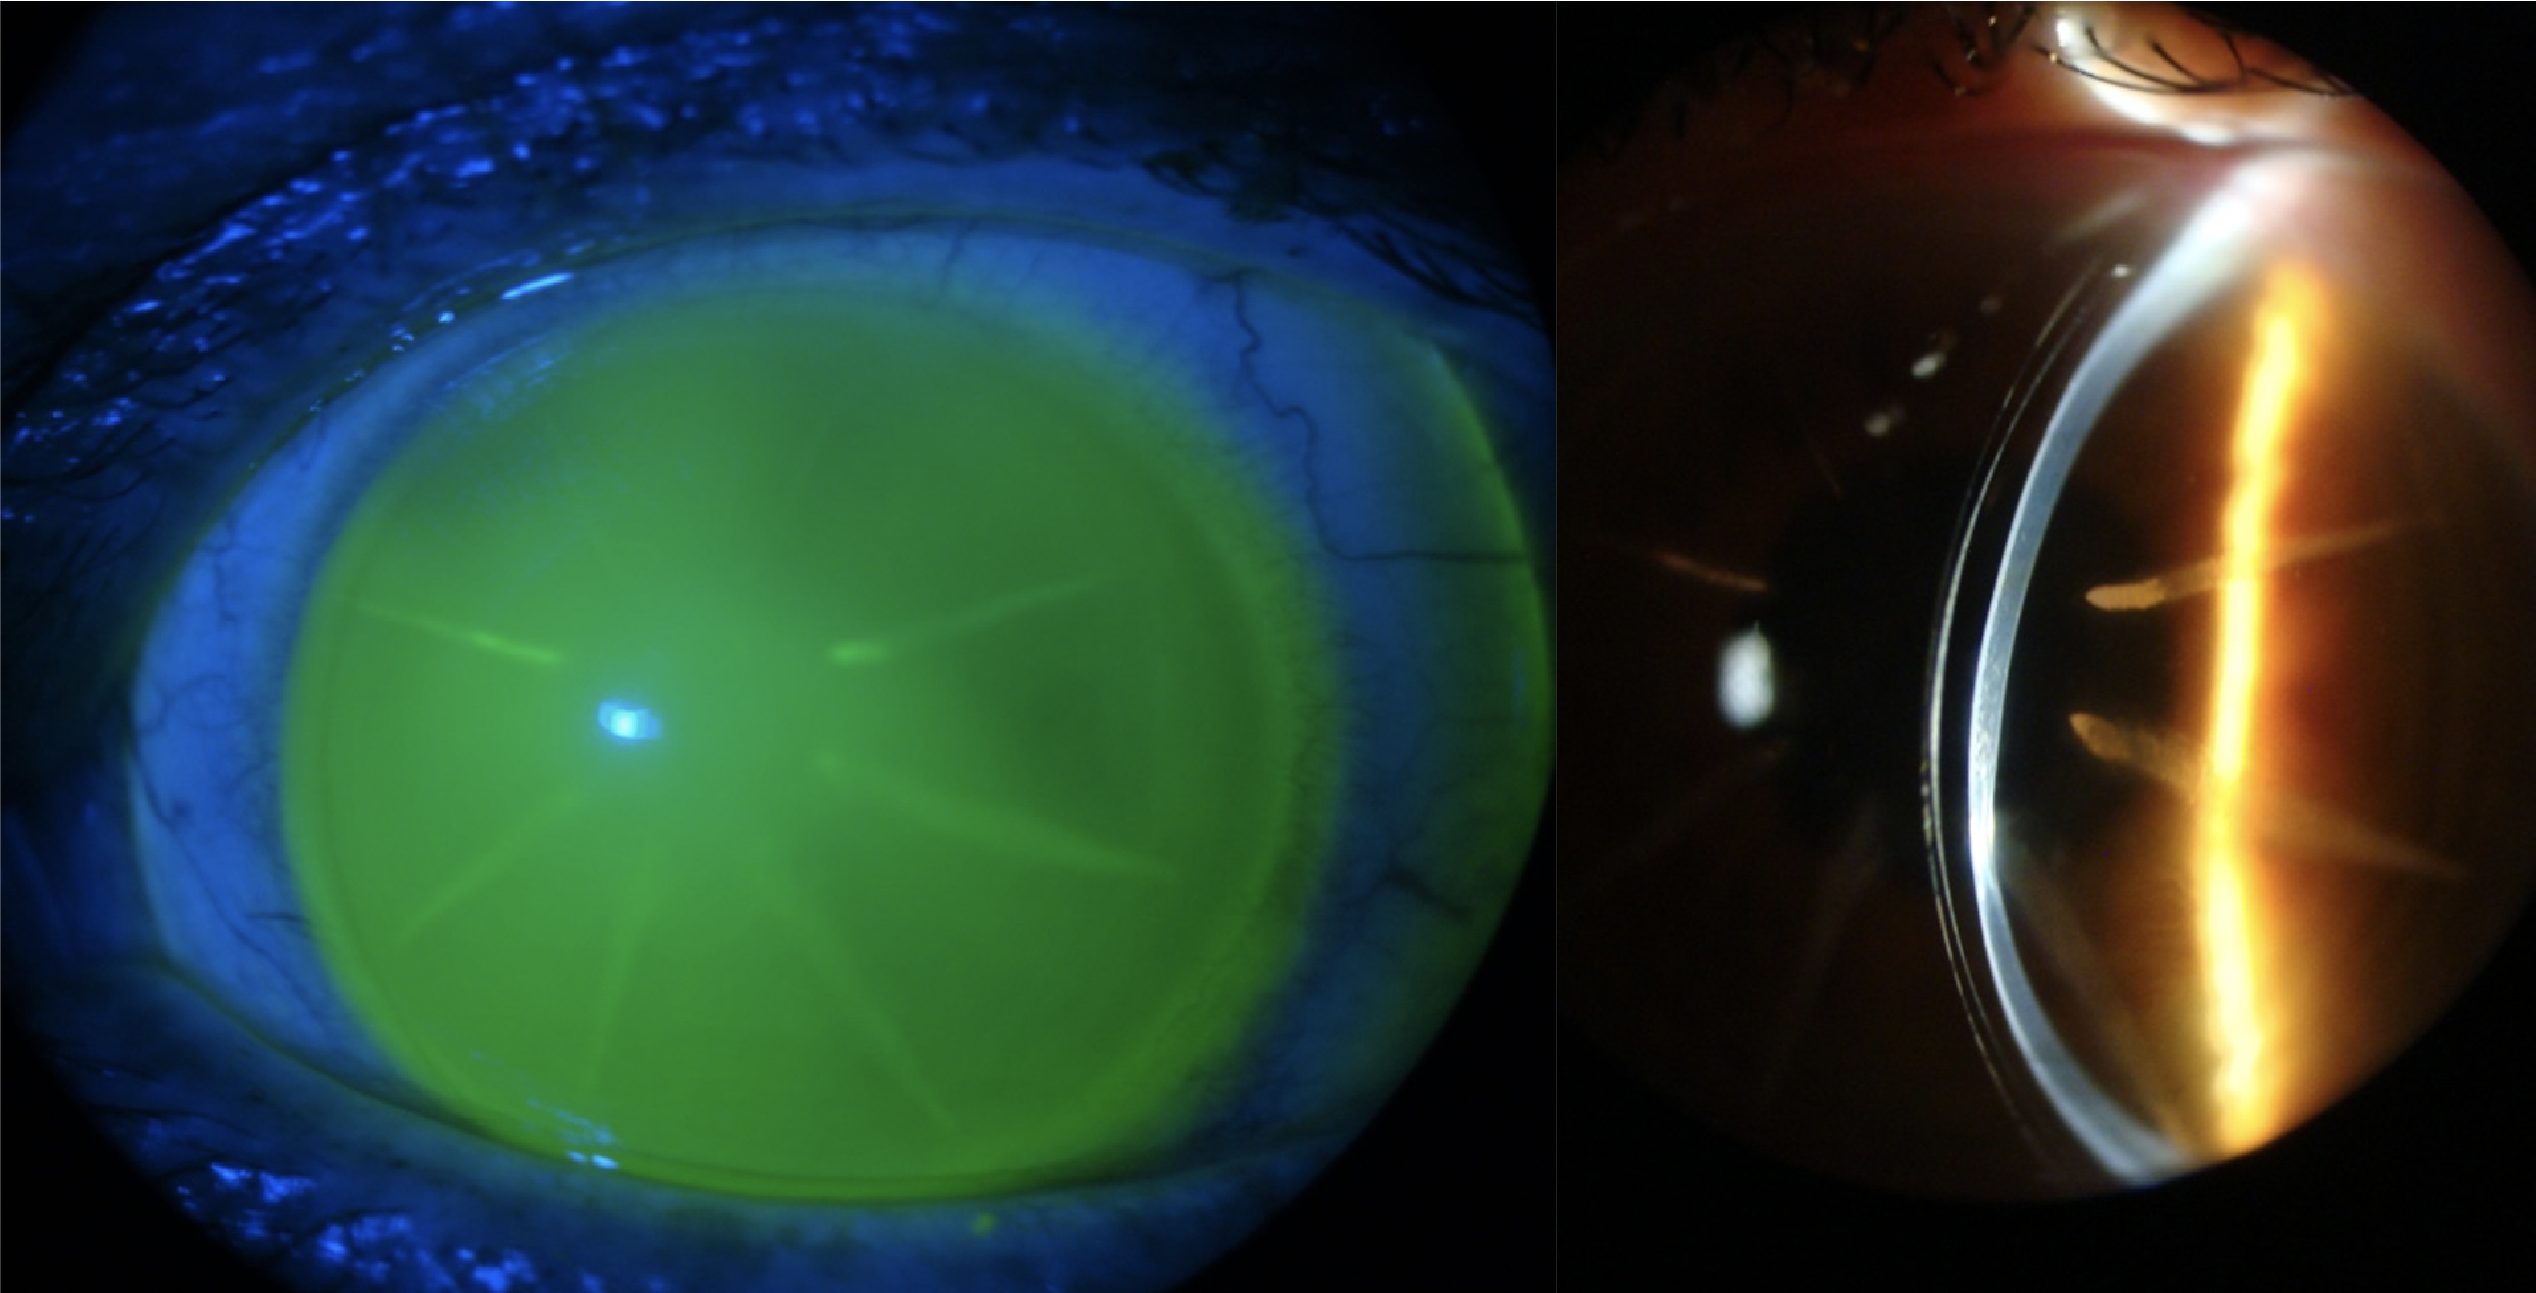
An attempt was made to flatten the haptics, modify the area along the mid-haptic portion to minimize mid-haptic compression and obtain better alignment. Despite these efforts, the patient continued to report pressure sensation with device wear and difficulty with device removal at the end of the day. These symptoms are traditionally associated with lens compression and suction with increased wear time. After reviewing the findings and the thought process with the patient, the decision was made to increase the lens diameter to 19.5mm to provide a larger surface area on which the device could rest. Figure 4 shows the new fitting endpoint with the 19.5mm, 8-meridian quadrant-specific device. One can observe good haptic alignment and the eye is white and quiet, with a nice and even distribution of lens clearance over the grafted cornea.
Reducing Suction and Maximizing Oxygen Permeability

Figure 4. Fitting endpoint with an 8-meridian, quadrant-specific 19.5mm PROSE device after PKP OS.

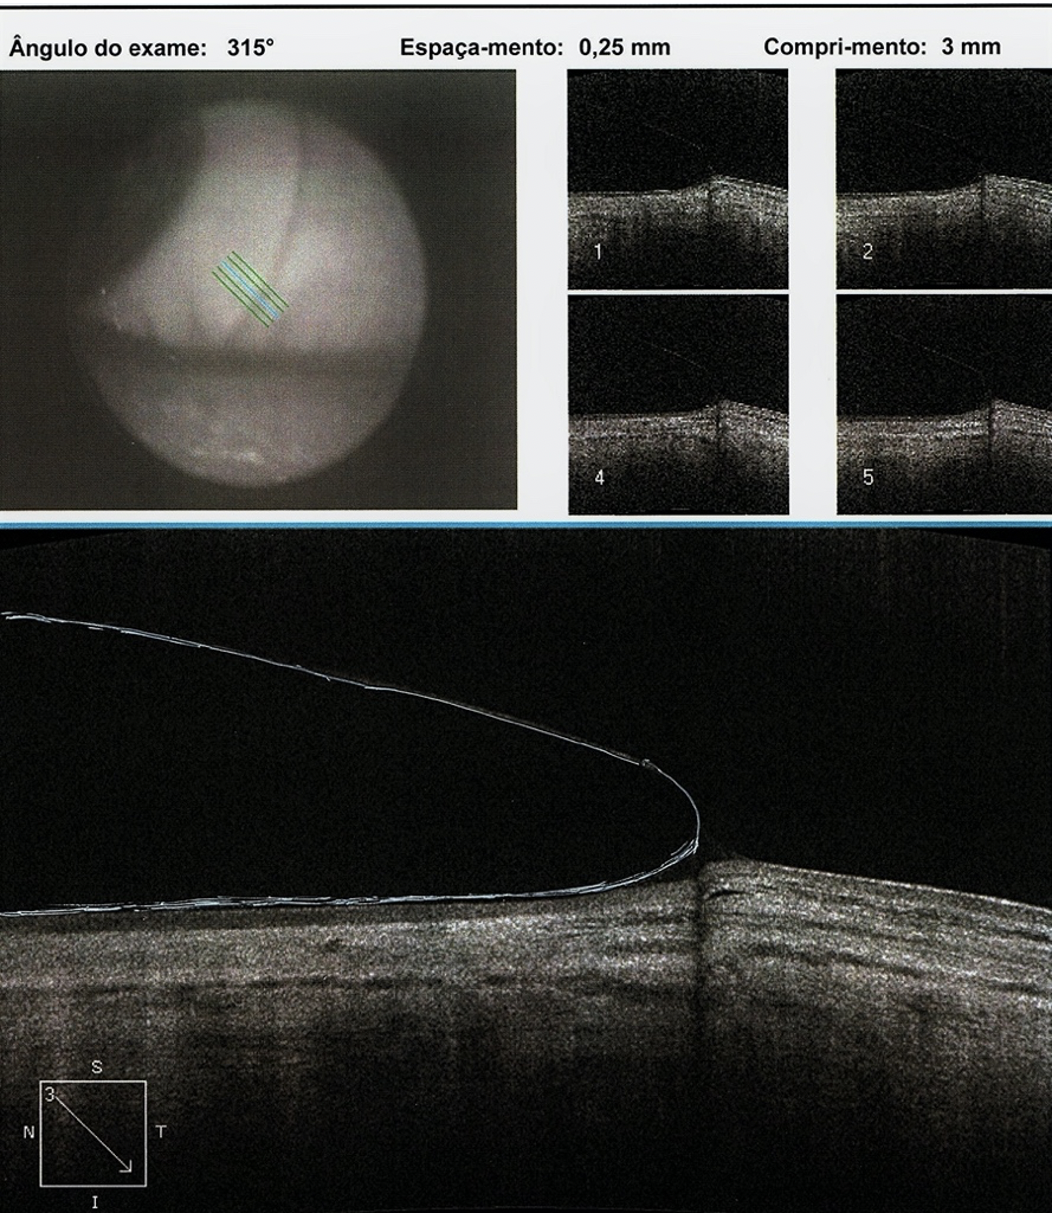
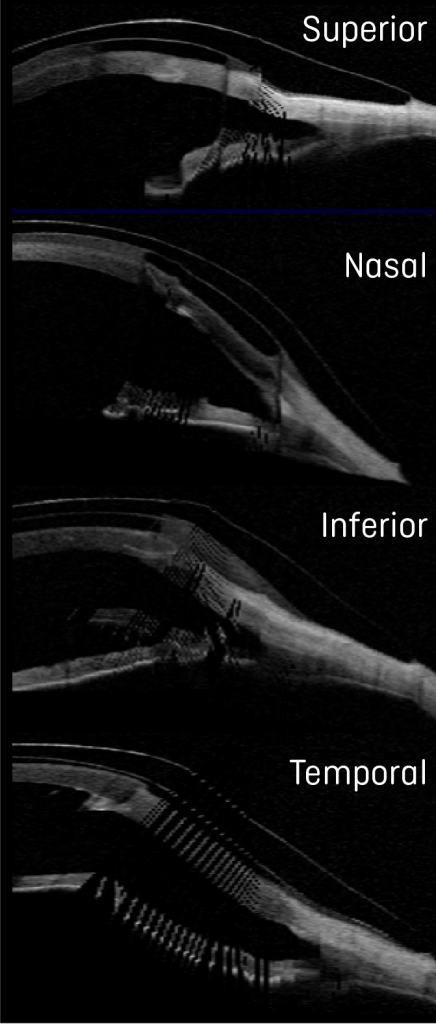
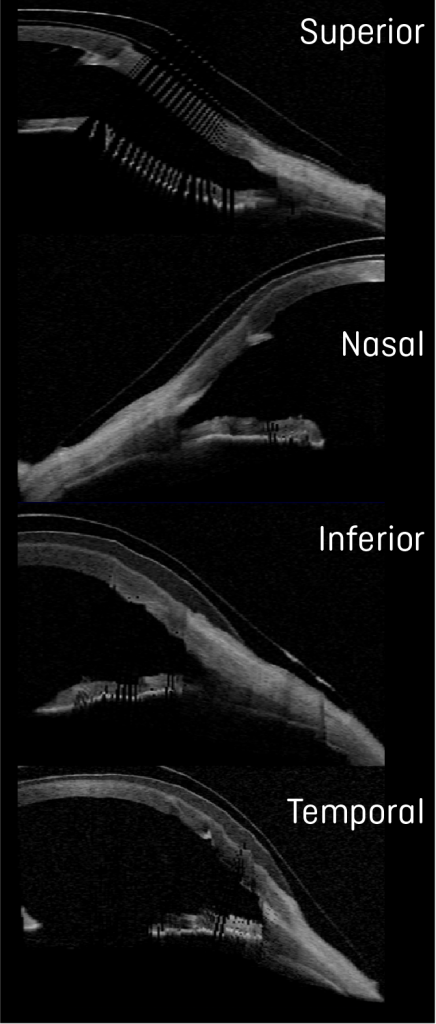
Comparison OCTs show the increased landing surface area when going from an 18.5 (Figure 5) to a 19.5mm device (Figure 6). This attempt to maximize weight distribution over a larger surface area has proven efficacious in our clinical practice when dealing with compression symptoms and device intolerance. While maintaining the same sagittal height, we additionally flattened the base curve to accommodate the more oblate nature of the cornea after transplant as shown in Figure 7.
Reducing Suction and Maximizing Oxygen Permeability

Figure 5. Ocular Coherence Tomography (OCT) of an 18.5mm device in the different orthogonal meridians of the left eye.
Reducing Suction and Maximizing Oxygen Permeability

Figure 6. Ocular Coherence Tomography (OCT) of a 19.5mm device in the different orthogonal meridians of the left eye.
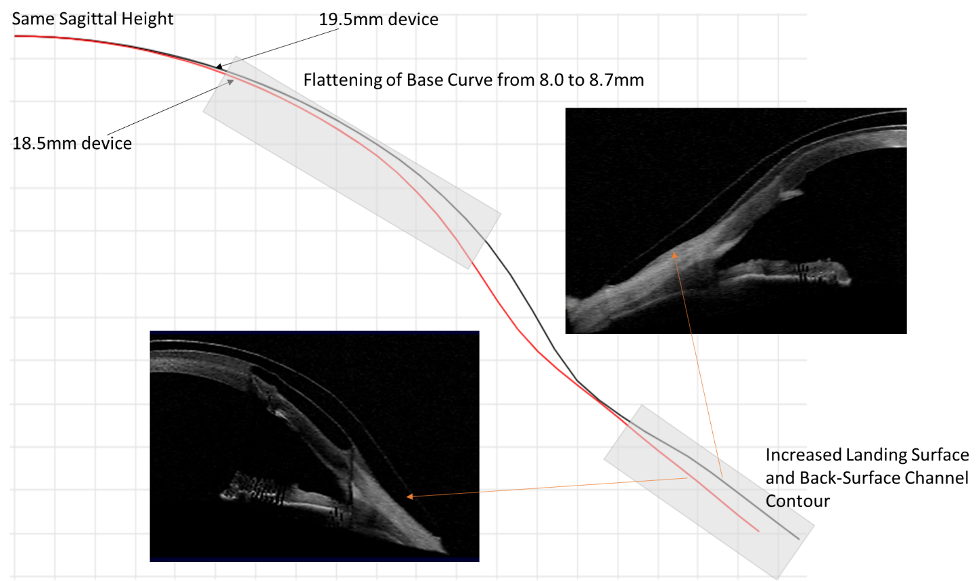
Figure 7. Graphical images of 18.5 and 19.5mm, juxtaposed to show the changes to the lens design based on parameter changes using spline curve technology and as observed by OCT. The nasal meridians corresponding to the flattest meridian in the eye are shown for comparison.

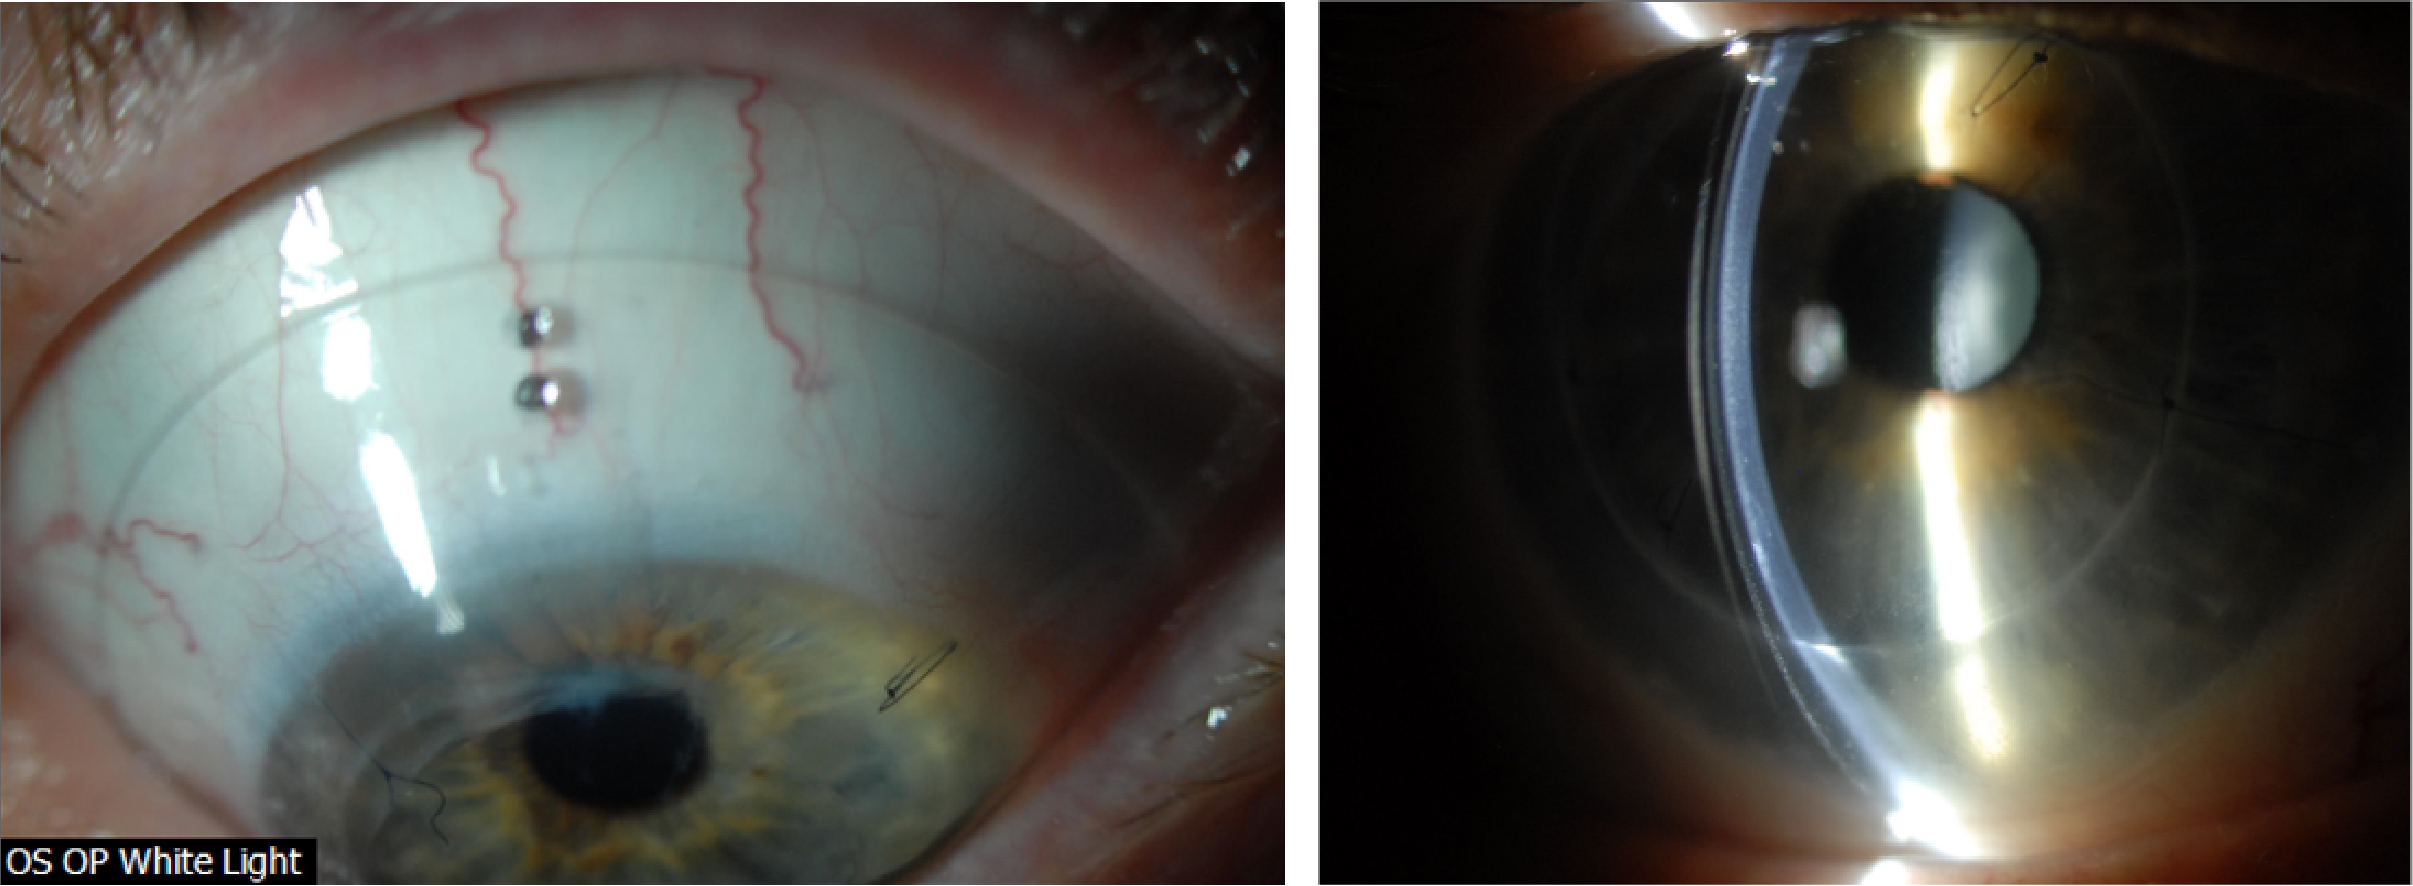
Interestingly, while we were optimizing the fit and after reporting improvement in comfort with increased lens size, the vision in the left eye dropped to the 20/50-20/60 range over the course of a couple of months. During all evaluations, we carefully monitored for signs of microcystic epithelial corneal edema, signs of rejection, etc. and at no point were evidence of these found. Given the history of previous cataracts and the fact the patient was on chronic low dose steroids, we performed an undilated assessment of the human lens in the left eye. Photo documentation revealed the development of a posterior subcapsular cataract (PSC) (Figure 8), which was later confirmed to be visually significant during dilated assessment by her corneal specialist. The patient decided to move forward with cataract extraction with hopes to improve vision.

Figure 8. Evidence of PSC formation, during undilated assessment.

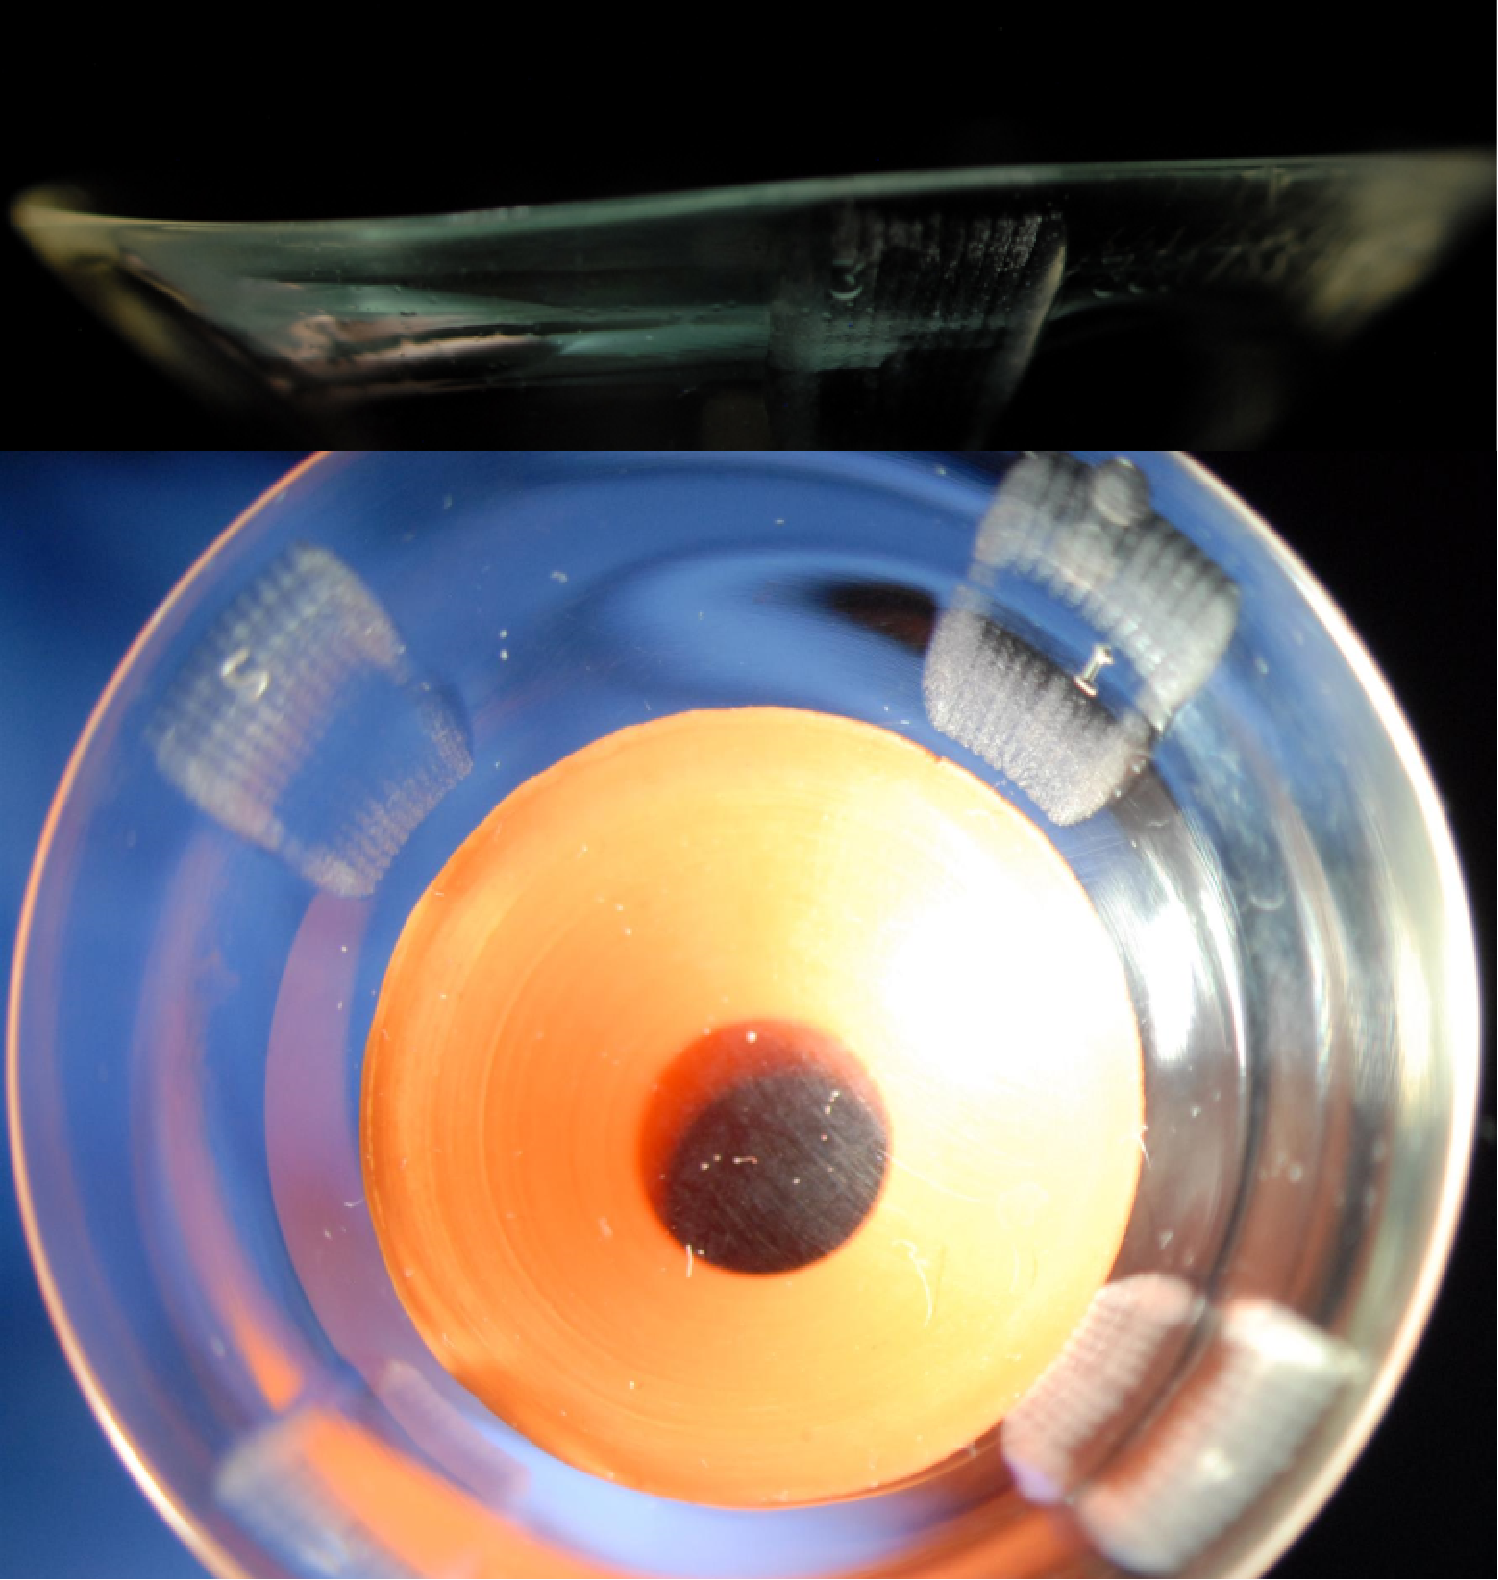
Before cataract surgery, we decided to challenge the current 19.5mm design hoping to obtain a comfortable and physiologically compatible lens design. After the patient wore the lens for one week, she reported that the previous symptoms of pressure and difficulty with lens removal had improved, but they were still present. To further minimize compression and suction symptoms, we added 4 back-surface haptic channels to soften further the landing of the haptic surface from bearing harshly on the conjunctiva and prevent a seal off effect (Figure 9).
Reducing Suction and Maximizing Oxygen Permeability

Figure 9. A 19.5mm, 8-meridian quadrant-specific PROSE device with the addition of 4 back-surface haptic channels to minimize suction and improve comfort.

Discussion and Final Outcomes

Long-term outcomes and benefits of scleral lenses after penetrating keratoplasty have been reported in the literature – while most patients benefit from improvement in visual acuity, complications with scleral lenses, i.e. microcystic corneal edema can ensue in this patient population.1 Special consideration should be taken when fitting or refitting grafted corneas with scleral lenses to minimize the risk of corneal edema, erosions and ultimate rejection. Strategies to promote fluid-ventilation like avoiding tight-fitting edges, lens seal-off and adding back-surface haptic channels can be especially important.1-5 Clinical practice has also shown that the addition of back-surface channels can have the potential to minimize lens suction over time and lead to improvement in physiological endpoints.5-7

In this case, with an increase in scleral lens landing surface area, customized haptic in an 8-meridian quadrant-specific manner and the addition of 4 back-surface haptic channels, not only are we promoting fluid-ventilation to optimize physiological endpoints, but we have a reported significant improvement in comfort. The choice to manufacture lenses in Optimum Infinite material potentiates the oxygen permeability to the grafted cornea. With the final lens after cataract surgery, the patient was able to achieve 20/25+2 best corrected visual acuity with an average comfortable daily wear of up to 12 hours.

By undertaking strategies to progressively soften the landing over the conjunctival surface to reduce or eliminate lens compression over time and minimize suction we were able to achieve a successful refitting outcome.


1. Severinksi, B. et. al. (2014) Scleral contact lenses for visual rehabilitation after penetrating keratoplasty: long-term outcomes. Cont Lens Ant Eye, 37, 196-202.
2. Rosenthal, P. Croteau, A (2005) Fluid-ventilated, gas-permeable scleral contact lens is an effective option for managing severe ocular surface disease and many corneal disorders that would otherwise require penetrating keratoplasty. Eye Cont Lens, 31(3), 130-134.
3. Severinksy, B et. al. (2010) Current applications and efficacy of scleral contact lenses – a retrospective study. J Optom, 3(3), 158-163.
4. Stason WB, Razavi M, Jacobs DS, et al. (2010) Clinical benefits of the Boston ocular surface prosthesis. Am J Ophthalmol, 149, 54–61.
5. Carrasquillo, KG, Byrnes, S (2018) Corneal edema and scleral lenses. Cont Lens Spect, 33, 34-41.
6. Barnett, M (2018) Mind the suction. Scleral Lens Monthly, Nov 2018.
7. Carrasquillo, KG (2020) Mind the suction II. Scleral Lens Monthly, Jul 2020.

Thank you to Dr Karen G.Carrasquillo for contributing to Global Insight.

[us_separator show_line=”1″ size=”small”]
[us_image image=”9526″]

Dr. Karen G. Carrasquillo is Vice President of Clinical and Professional Affairs at BostonSight. In addition, she is an adjunct clinical professor at the New England College of Optometry, an adjunct clinical professor at the school of optometry, MCPHS University, Advisory Board member for the Gas Permeable Lens Institute (GPLI), Fellow of the American Academy of Optometry (FAAO), Fellow of the Educational Society of Scleral Lenses (FSLS), and Fellow of the British Contact Lens Association (FBCLA). She is the founder and Program Chair of FitAcademy, an educational retreat for Cornea and Contact Lens Residents, and is also a planning committee member for the International Congress of Scleral Contacts (ICSC) Meeting and Global Ophthalmic Women (GLOW) meeting.
[us_separator show_line=”1″ size=”small”]
[us_post_navigation in_same_term=”1″]
[us_sharing providers=”facebook,twitter,linkedin” align=”right”]
Tags: , , , , ,

Scleral Lens Fitting Post-Refractive Keratotomy

[us_post_title][us_post_date][us_separator size=”small”]

by Luciano Bastos

Summary

Patient male, 46 years old, army official, history of post-refractive keratotomy OU performed in 1994, visual acuity was good until 2014 when it began to deteriorate. The patient had to retire early due to his condition and then began to practice law as an army lawyer. He had been wearing glasses which gave poor quality of vision and reduced acuity. He came to us from another state after visiting several doctors and testing different contact lenses in an attempt to improve his vision.

He was fitted with full scleral lenses and the results were an optimal fitting relationship, great comfort and excellent visual acuity while also preserving anterior eye and corneal physiological health.

Introduction

Our clinic has a long history of fitting irregular cornea conditions and since the early introduction of refractive radial keratotomy, many patients were referred to us in order to restore vision in cases where soft lenses or spectacles would not offer satisfactory results. During the early 90’s we relied upon the 12.7 mm wide RGP intra-limbal designs to provide the larger overall diameter to resolve cases like this. It was always a challenging process but our efforts did help many patients.

By 2014 we were able to utilise a full scleral lens design we developed after many years of research into the manufacturing and fitting of scleral lenses. My father, Dr Saul Bastos, MD asked me to study scleral lens technology and suggested that I contact his professor and friend Dr Perry Rosenthal, MD PhD (US) who became my mentor on the subject for years. I also relied on a great friend and specialist in the UK, Dr Ken Pullum FC Optom DipCLP.

During the first experimentations on manufacturing scleral lenses in 2006, we only were able to manufacture up to 16.0 mm. In the following years, new materials and diameters were available which allowed us to manufacture scleral lenses as large as 21.0 mm. There are some cases in which large, full scleral lenses are necessary, especially when there is a disease like dry eye or a large cornea with a large palpebral aperture.  

In this case, we faced an irregular corneal condition with a large cornea and palpebral aperture which clearly needed a higher SAG and a wide landing zone. The fact that it was a post-surgical cornea that had been damaged by incisions and now had scars together with reduced mechanical strength due to damage to the collagen fibres also made me aware of the importance of oxygen delivery to the cornea. At the time of the fitting, we were working with the Optimum Extreme (125 DK) from Contamac, it was reassuring to be able to rely on a higher oxygen permeability as this case required full scleral lenses.    

Examination

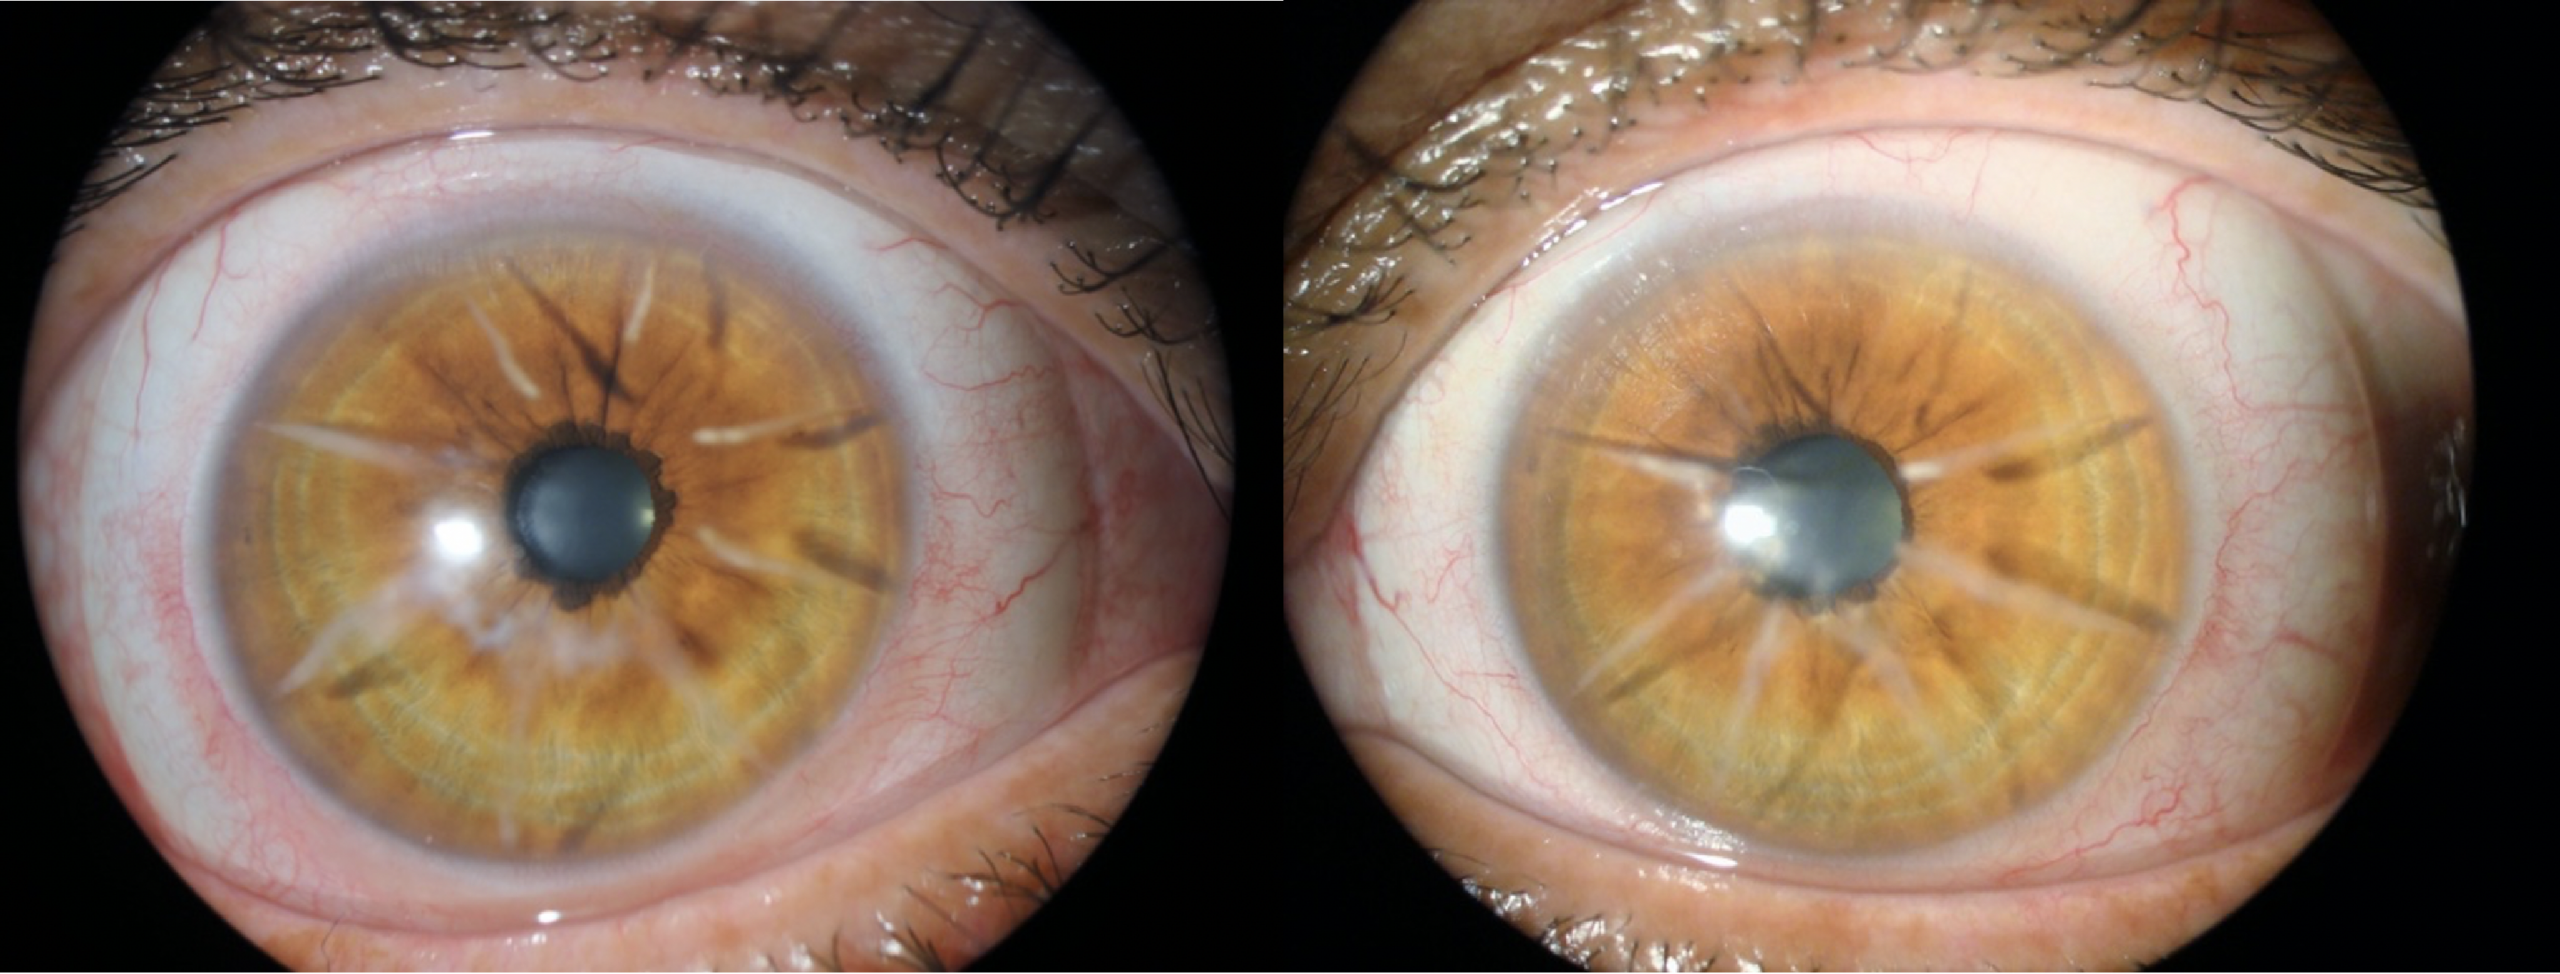
Biomicroscopy showed a series of eight radial incisions with significant depth OU and flatter topography at the central cornea. A decreased corneal thickness was also observed at the central and paracentral cornea. The slit-lamp cross-section view showed an abnormal corneal profile (Figures 1 to 4).

Scleral Lens Post-Refractive Keratotomy

Figures 1 and 2: OD radial incisions and irregular cornea profile under slit-lamp.

Figures 3 and 4: OS radial incisions and irregular cornea profile under slit-lamp.

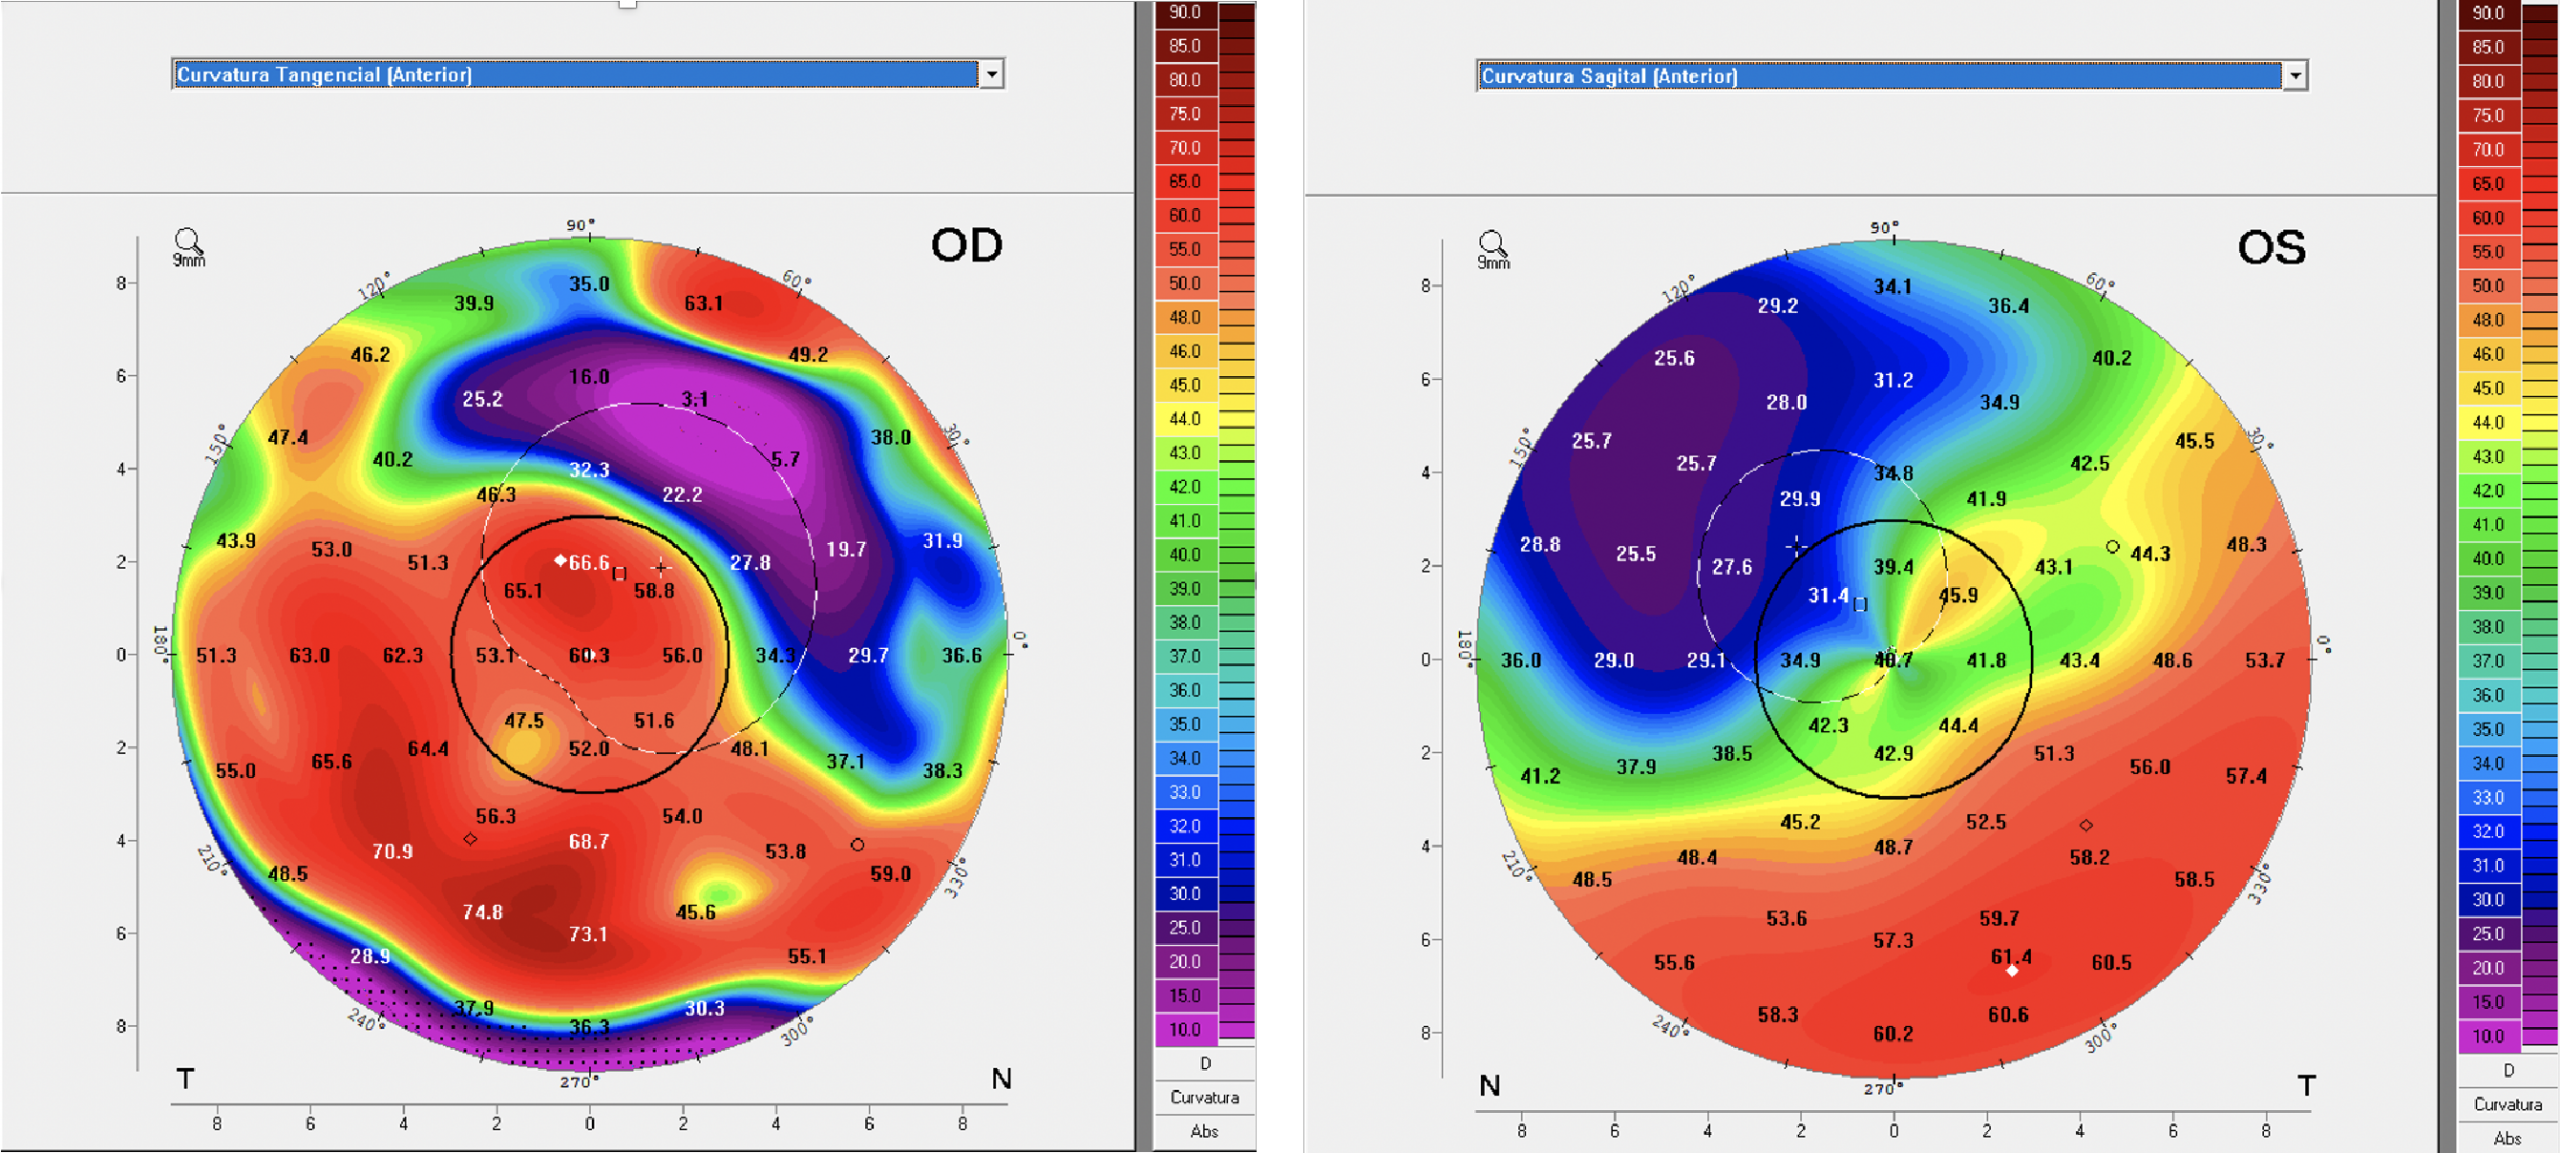
Endothelial cell count was lower than normal in both eyes, worst at OD, so we definitely would need a high Dk, a full scleral lens design and the system I developed called Wave Spline Technology (WST). WST is a ventilation channel system that allows tears to enter the fluid lens reservoir to help to deliver more oxygen to the cornea. We also performed a Pentacam Scan (Figures 5 and 6) and collected data from the precise maps this technology offers together with an OCT to verify each and every quadrant to optimise the landing haptic for a gentle and smooth fitting.    

Anterior Sagittal Curvature

Figures 5 and 6: Anterior Sagittal Curvature large maps.     

The patients that submitted to corneal refractive procedures were normally higher myopes and the larger amount of correction required necessitates deeper and more numerous incisions. Back in the day when this procedure was performed, the initial protocol was four radial incisions and, if additional correction was needed, an extra four radial incisions were made. I remember being in an ophthalmology congress with my father, Dr Saul Bastos, at which some surgeons were debating this technique and one of them said that he would perform a total of 12 or more incisions. That was really surprising to my father and me, as we were seeing those patients with those outcomes.

The procedure was abandoned with the advent of laser technology, which also has its complications. The reason I highlighted high myopia is that these patients should be carefully evaluated for glaucoma and retinal diseases as they are more prone to have posterior eye complications. Dr Marcelo Bittencourt MD (IOSB clinical director) examined the patient as a standard procedure with awareness that he was a high myopic patient before refractive surgery.      

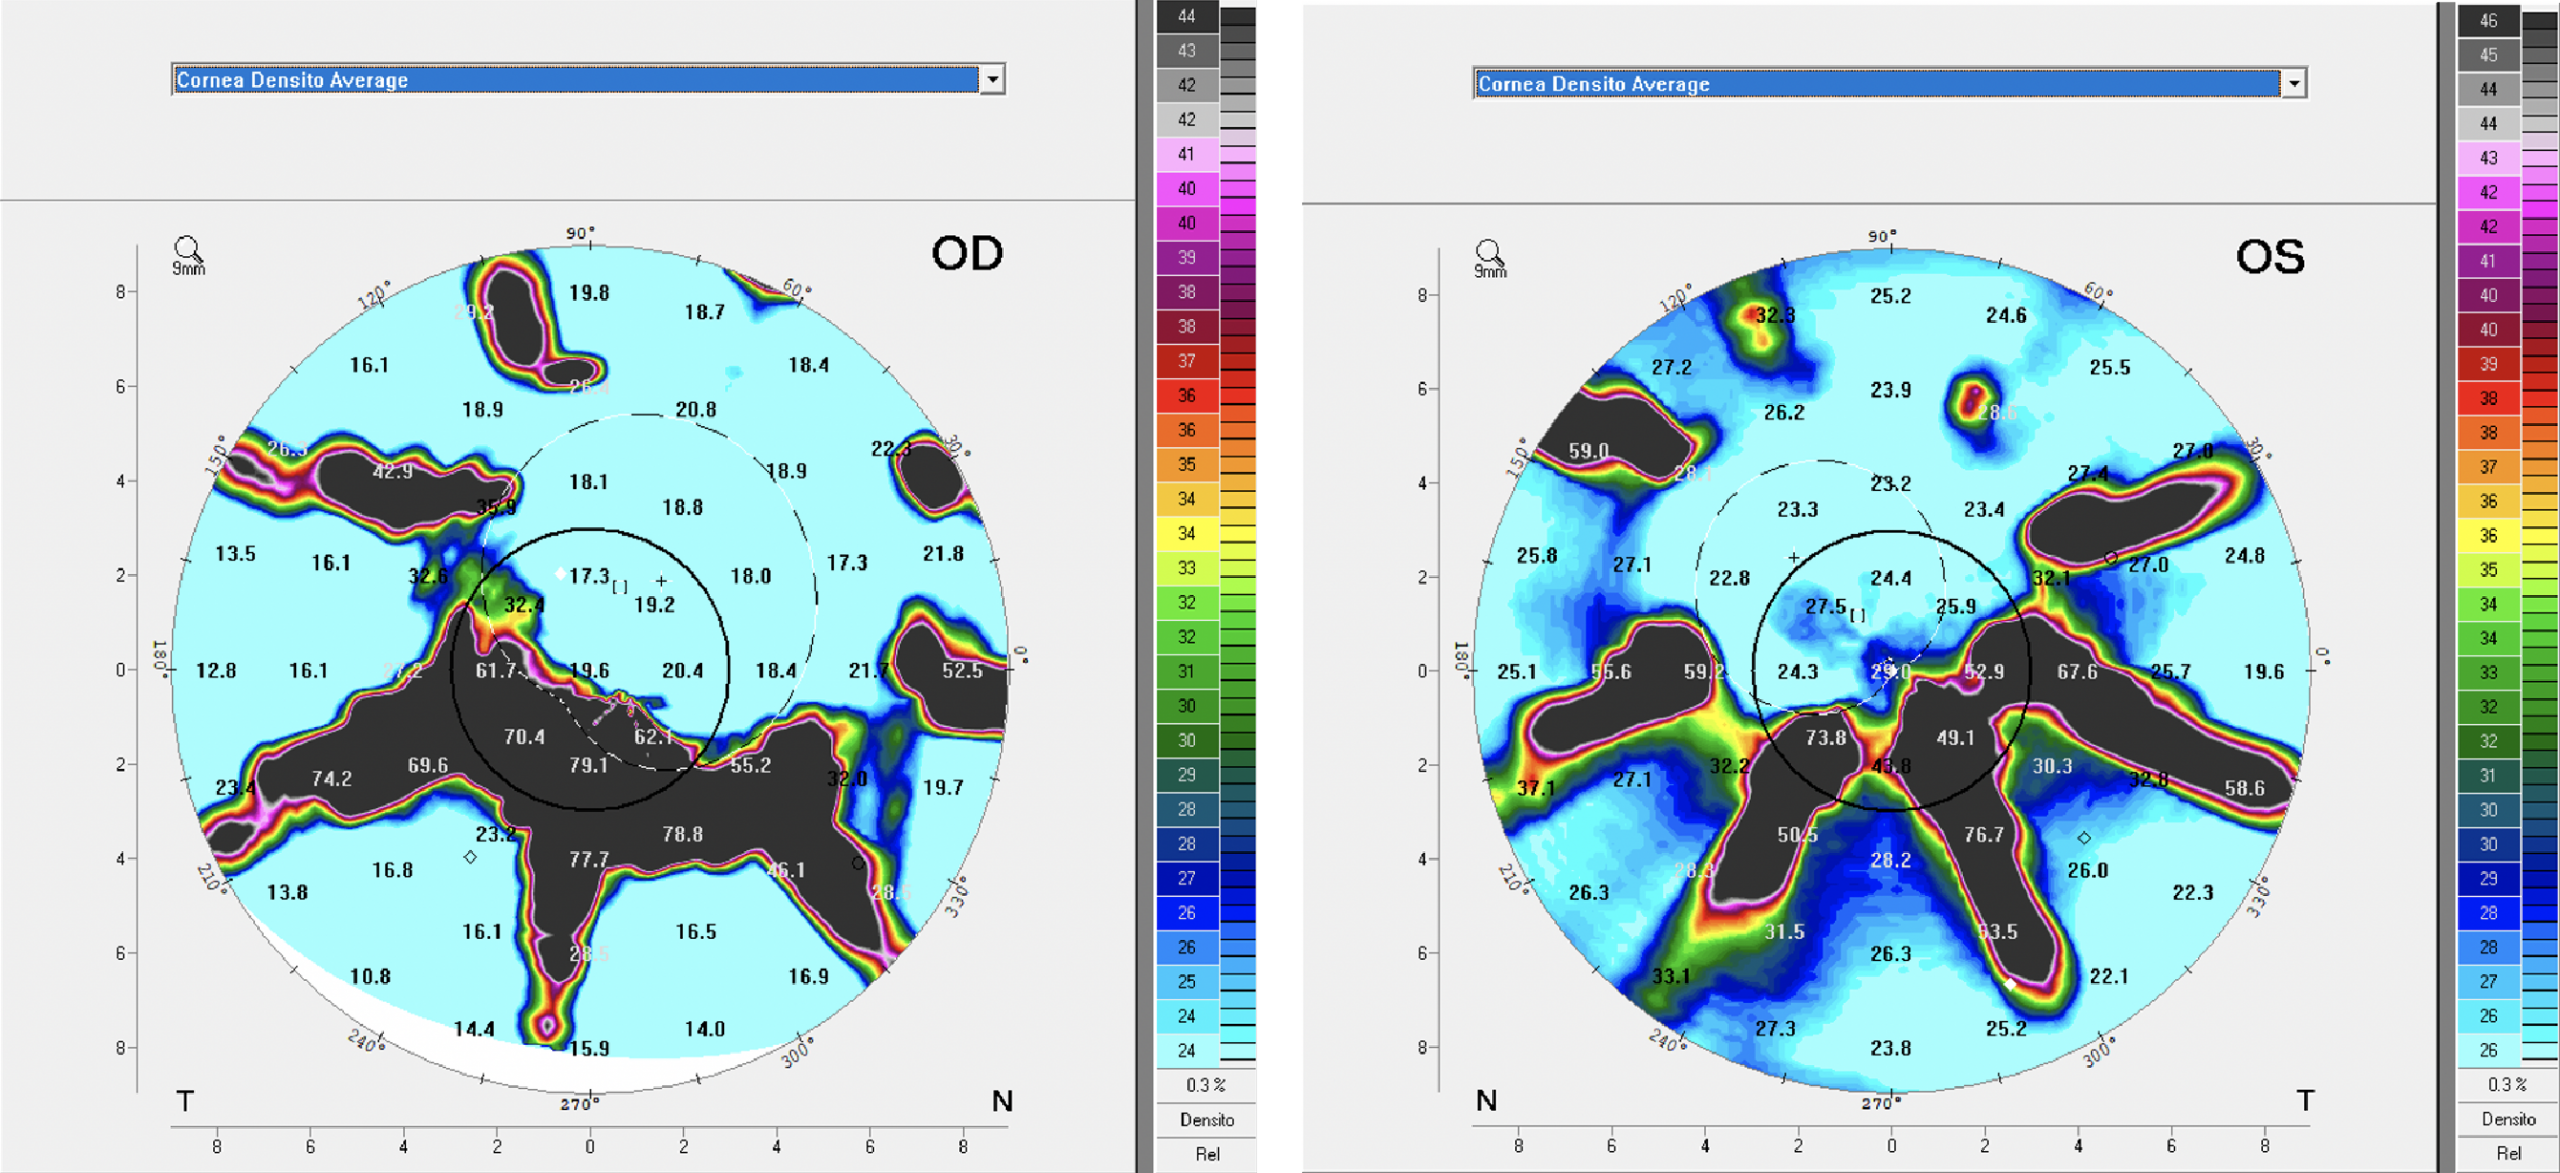
With the Density Average map from Pentacam (Figures 7 and 8), we can also observe the areas of the incisions (in black) with severe opacities. These areas also show the extensions of the incisions and its impact on the corneal epithelium and the corneal topography. The densitometer screening also helps to identify if corneal opacities or haze would change in subsequent examinations.   

Density Average maps

 Figures 7 and 8: Density Average maps identifying opaque areas at the incisions.

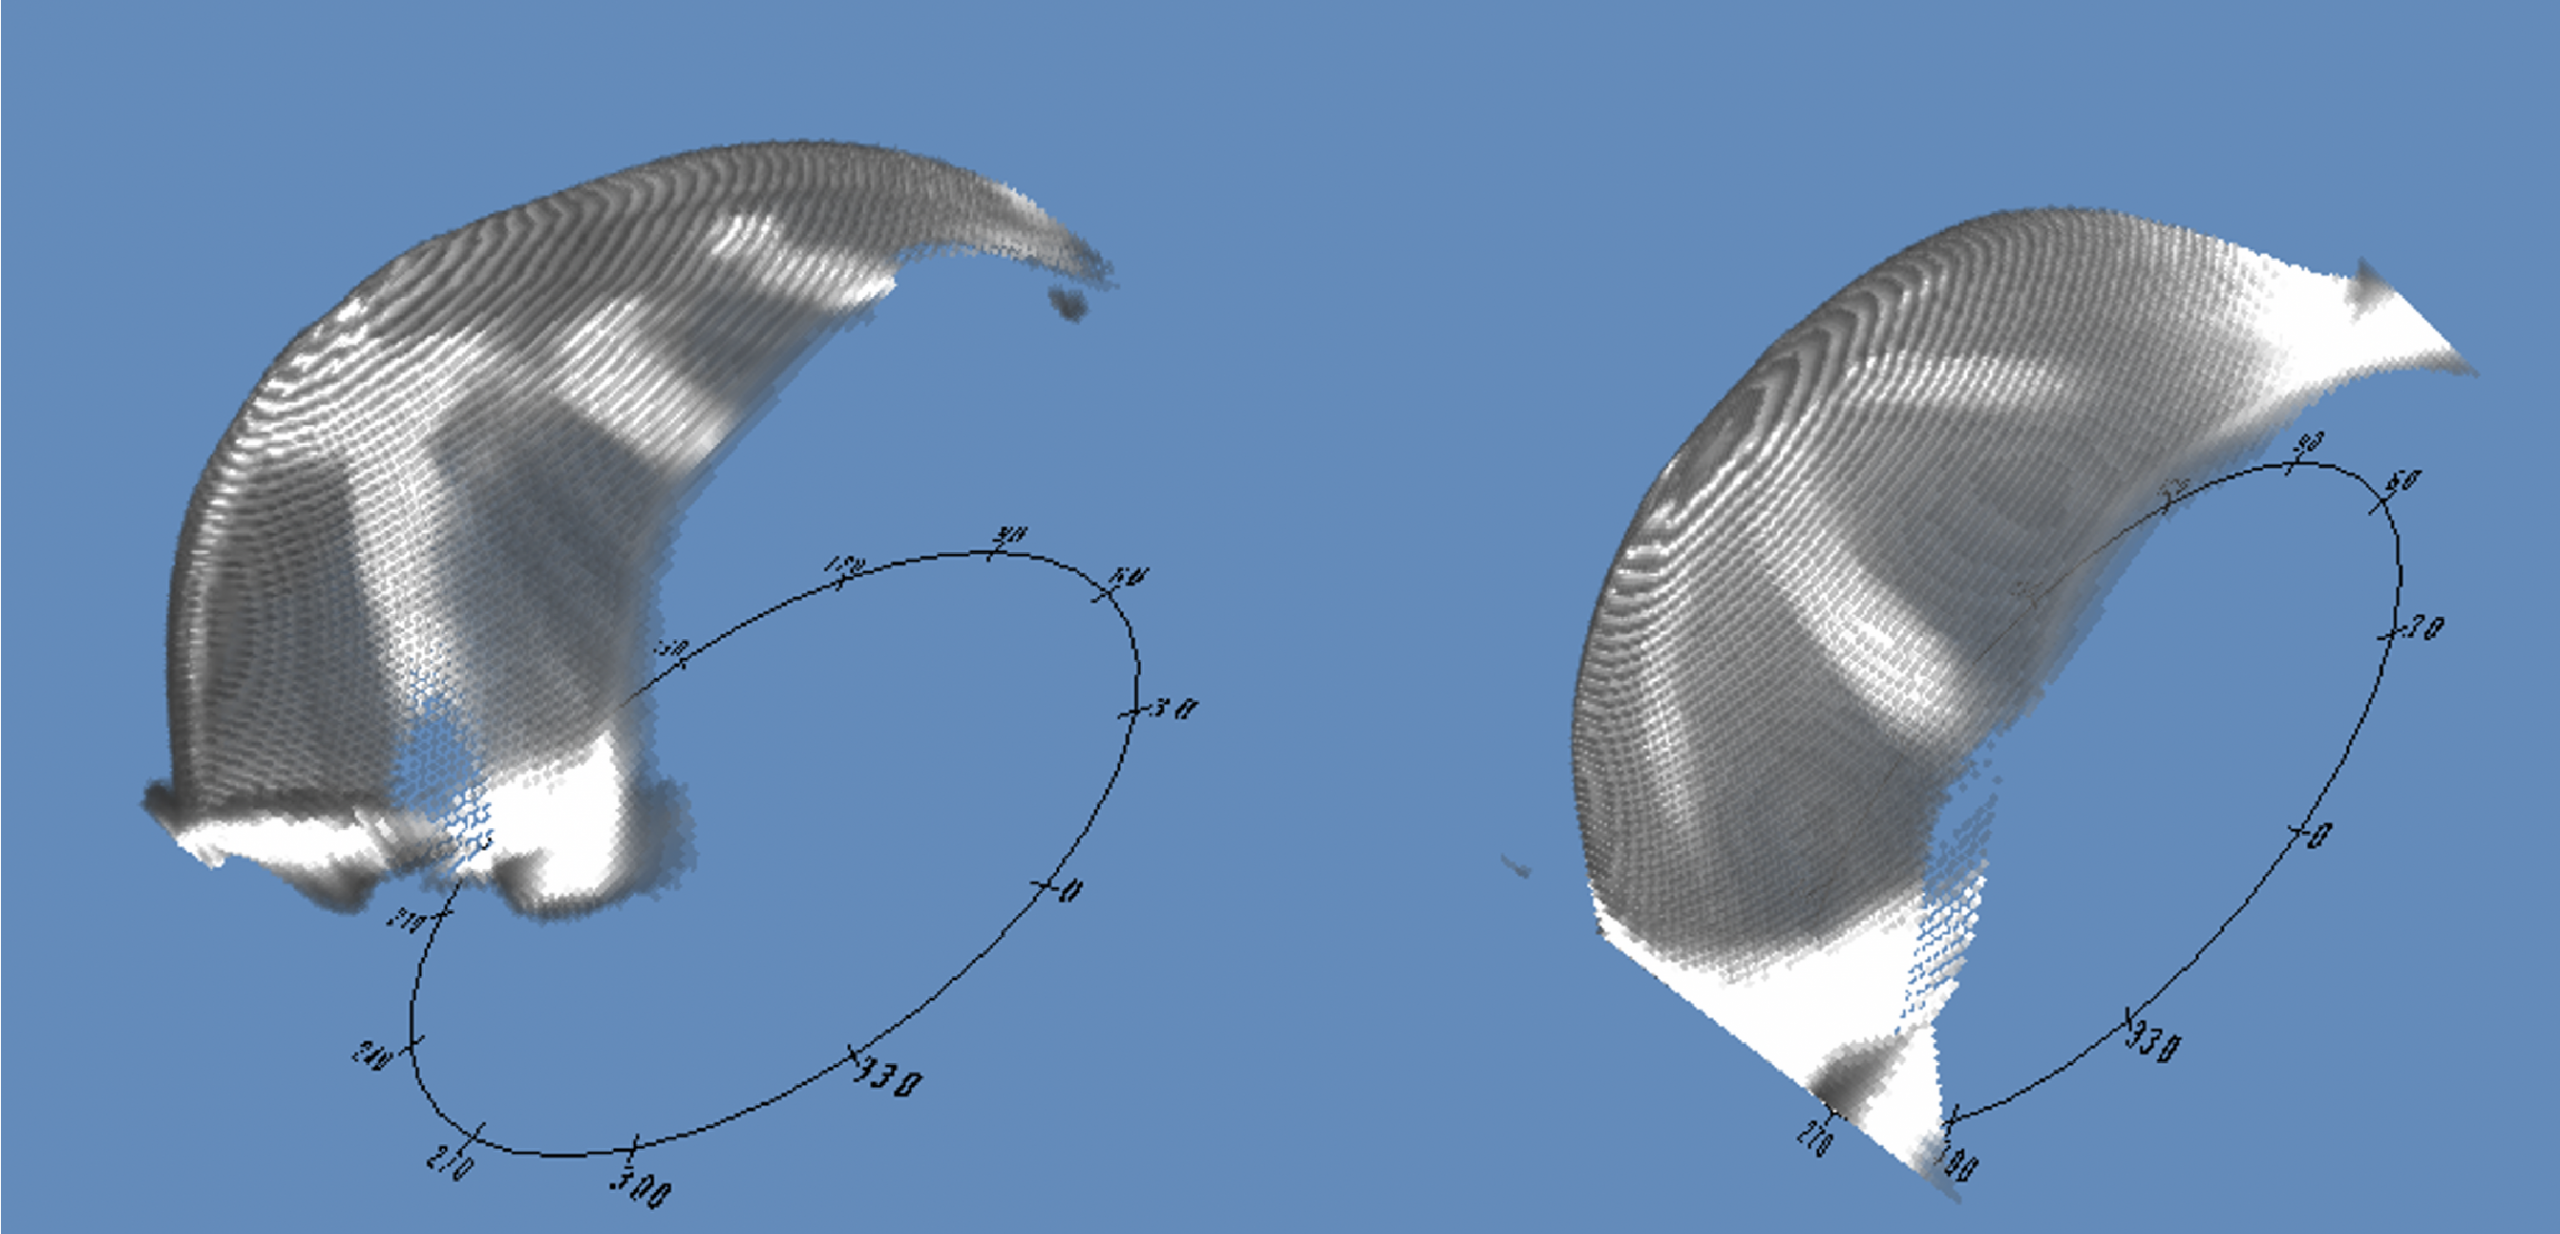
The Scheimpflug and the 3D model images are also great tools to examine abnormal cornea conditions with high irregular astigmatism. The Scheimpflug is similar to the cross-section-view on the slit lamp but it can show the cross-section in different angles. The 3D cornea model is capable of giving a better comprehension of the overall aspect of the anterior cornea and also is capable of showing areas of opacities, it can be rotated in real-time so you can view it from different perspectives, (Figures 9 and 10).

3D Corneal Model images from Pentacam

Figures 9 and 10: The 3D Corneal Model images from Pentacam, OD and OS.

We do not hesitate to use all the technology we have to get a comprehensive understanding of the case and data we can use to achieve the best possible speciality lens fit.

Contact Lens Examination and Fit Evaluation

This patient was fitted for the first time in 2014 with 19.6 mm scleral lenses. He wore the lenses for three years with no complications and came for a refit in 2017. Both fits were with the Optimum Extreme material (125 Dk).

In 2019, the patient came for a follow-up and I discussed the new Optimum Infinite material from Contamac that has a Dk of 180. The patient was happy to know more about it, and subsequently, he was refitted with the Optimum Infinite material. The lens parameters were: 

  OD OS
BC 47.50 x 45 (7.10 x 7.50) 44.00 (7.67 mm)
Power -15.00   -8.50
OAD 19.6 mm 19.6 mm
SAG  7.711 7.270
Material Optimum Infinite Optimum Infinite
Scleral Lens Post-Refractive Keratotomy

Figures 11 and 12 front images of the model SB Full Scleral lens, OD and OS.

Observe OD the enlarged opacity below the pupil, also visible in the density average map from Pentacam (Figures 7 and 11). The OS image (figure 12) also shows the visible incisions from the refractive keratotomy and it also can be compared to the Density Average image (figure 8) from Pentacam.

Initial thoughts were to design a reverse scleral lens design with a flatter posterior central base curve and a secondary, steeper base curve to overcome the flatter pattern at the central cornea. However, we were able to fit a double base curve, adjusting the base curve radius and optical zone diameters to achieve a good fit on OD as seen in figures 13 and 14.

At OS we designed a single base curve with a large optical zone diameter and we could overcome all the elevations on the cornea (Figures 15 and 16). Both eyes were fitted with a SAG that proved to be high enough after settling with four hours of lens wear. The frontal and cross-section view observed and the slit lamp shows the fluid lens reservoir at both perspectives.     

Scleral Lens Post-Refractive Keratotomy

Figures 13 and 14: OD frontal and cross-section view on the slit lamp with fluorescein.

Scleral Lens Post-Refractive Keratotomy

Figures 15 and 16: OS frontal view with fluorescein and cross-section view with white beam.

The patient was happy with the comfort, and visual acuity was 20/10 J1 OU. The visual outcome was much better than expected despite the fact he is 46 years old, (so he should be entering presbyopia soon) he was able to read J1 with no add correction. He was informed about the possible future need of add correction, we determined his dominant eye for possible near vision correction when necessary, utilizing reading glasses, monovision or a multifocal design in the early stages.          

We also performed an OCT scan at eight different angles to have a better understanding of the landing pattern in each meridian. The scans were separated by each angle; one image of the limbal transition and the other of the landing haptic including the edge as you can see in figure 17.

The OCT exam is a great tool to identify areas where the haptic may present significant pressure over the conjunctival sclera, or excessive lift. With all information gathered from these 16 images generated by OCT we can plan and design the scleral lens with an estimation of toricity that we may apply to the haptic and align where required.

Scleral Lens Post-Refractive Keratotomy

Figure 17: A single segment of the haptic showing scleral alignment.

Follow-up Visit After 120 Days

During the weeks following the dispense, the patient reported feeling good, with excellent vision. After about 120 days of dispensing, he was able to visit us again, bearing in mind he lives in another state.

Biomicroscopy during examination showed a crystal-clear cornea, specular biomicroscopy remained stable with a similar endothelial cell count. Visual acuity also remained stable and there was no sign of corneal edema or any complications. Our normal procedure during follow-up visits is to re-evaluate the fitting and consider what might be required to improve the overall fitting. In this case, we decided that with the next lenses we would increase the landing zone and also slightly augment the transitional limbal zone from the base curve to the haptic landing zone. This will allow the lens to have a better pattern over the limbus as it appears to be too close to the limbus (figures 13 and 15).

Customising the Scleral Lens Fitting

When we change any variable at the posterior curve, the optical zones and the overall diameter of the scleral lens SAG are affected. The more variables you change the more impact it has on SAG value, achieving a lower or a higher value depending on the changes made. If you have, like in this case, a SAG that you have as a reference it is a great starting point as you will need to apply the changes to customize the fitting. So, it is necessary to control these variables in a manner that the changes will result in a better fitting relationship while preserving the SAG value to a number close to the reference.     

This is absolutely true with trial lenses as well; we always think about customizing the fit whenever it is necessary. If the practitioner does not have software to calculate these changes it is of utmost importance to have technical assistance from a lab consultant that may be able to provide the possible calculations to achieve the results the specialist wants. Another possibility is to use what Ultralentes call Digital Consultancy. In this case, the doctors are encouraged to produce frontal and cross-section view images through the slit-lamp and forward these photos or short videos to the lab. This is often the case as practitioners generally do not use contact lens software to design lenses. Ultralentes also provide the practitioners with a Consultancy Form that the doctor may fill and also make observations and drawings of the specific areas he wants to improve from the trial lens used. 

Conclusion

The patient reported feeling really great with his new lenses, he mentioned that he was happy to change to a higher Dk material (Optimum Infinite). He reported greater comfort, visual acuity remained stable and the eye calm. The overall fitting was quite acceptable for a surgical cornea that has multiple incisions that had deteriorated the corneal physiology over the years.             

We know that patient’s previous lenses were made in Optimum Extreme and were worn for two years, they were fine and the motive for a new fit was based on taking advantage of higher oxygen transmissibility rather than necessity. Although the lenses were still acceptable to wear, naturally, a new pair may impact visual quality as acuity had no change. What is important is that after four months of wearing the new material, the results were clinically excellent and the patient was happy with comfort and vision.             

I also want to address that we had no problem manufacturing these full scleral lens designs in the Optimum Infinite material. It proved to be stable with excellent physical properties with a 180 Dk. This is really important especially when these speciality lens designs are planned.

At the time of writing this case, we already have several scleral lens fittings with Optimum Infinite and it is definitely a great and reliable material from Contamac. The higher Dk material for scleral lens patients means an extended wearing time but is especially important to post-surgery patients.

Here at the Instituto de Olhos Dr Saul Bastos (IOSB), 96% of the fittings are speciality RGP and scleral lens fittings. From these, about 70% are ectasic patients, including (most) keratoconus patients, pellucid Marginal Degeneration and keratoglobus. About 15% are post-surgical patients like post-penetrating keratoplasty (corneal transplants), post-radial keratotomy and post-laser surgery (Lasik and PRK), about 5% are dry eye patients. The remaining 10% of patients are moderate to high myopics, hyperopics, and aphakics. The introduction of the Optimum Infinite material is a great advantage to these post-surgery patients and those with the larger full scleral lens designs.  


1. Banta JT. Ocular Trauma – Bascon Plamer Eye Institute. Miami, FL – Saunders Elsevier, 2007
2. Black CJ, Rosenthal P, Kaufman HE et al. Symposium on Contact Lenses. Transactions – New Orleans Academy of Opthalmology. St Louis: Mosby, 1973
3. Bowden TJ. Contact Lens: The Story – Cornwall, UK. London: Bower House, 2009
4. Cochet P, Amiard H. Contact Lens International Clinics. Boston: Little, Brown, 1969
5. Cvintal T, Munarin MAM, Moro F. Complicações do Transplante de Córnea. São Paulo, Santos, 2004
6. Duker JS, Macsal MS, Fontes BM. Anterior Segment – Rapid Diagnosis in Ophthalmology, St. Louis, Mosby Elsevier, 2008
7. Girard LJ, Soper JW, Gunn C. Corneal and Scleral Contact Lenses. Proceedings of the International Congress. St. Louis: Mosby, 1967
8. Girard LJ, Soper JW, Sampson WG. Corneal Contact Lenses. St. Louis: Mosby Co. 1970
9. Godinho C, Dantas B, Sobrinho M.et al. O Padrão CG em Lentes de Contato. Bastos, L. Cultura Médica;. pág. 301 a 313. 2010
10. Jenkin L, Tyler-Jones R. Theory and Practice of Contact Lens Fitting: Hatton Press 1969
11. Pena A. Bastos, S et all, Clínica de Lentes de Contato. Cultura Médica, 1989; pág. 69-79
12. Philips AJ, Speedwell L, Morris J. Contact Lenses – 5th ed. Ed Butterworth Heinmann Elsevier 2007
13. Ferrara, Paulo.  Anel de Ferrara – Cultura Médica – 2006
14. Romero-Rangel T, Stavrou P, Cotter J et all. Gas Permeable Ocular Prosthesis Therapy in Ocular Surface Disease. Am J Ophthalmology, 2000, 130: 25-32
15. Rosenthal P, Cotter JM, Treatment of Persistent Epithelial Defect with extended wear of a fluid-ventilated gas permeable scleral contact lens Am J, Opthalm 2000; 130: 25-32
16. Rosenthal P., Cotter JM. The Boston Ocular Surface Prosthesis in the management of Severe Ocular Surface Disease. In: Foulks G. (ed.) Ophthalm Clin A Am 2003; 16: 89-93
17. Schein OD, Rosenthal P, Ducharme C. A Gas Permeable Scleral Lens for visual rehabilitation. Am J Ophthalmol, 1990; 109:318        
18. Fadel, Daddi DOptom, FSLS, FBCLA, FAAO – Scleral Lens Issues and Complications: Their Recognition, Etiology and Management. – Dougmar Publishing Group Inc. August 2020

Thank you to Dr Luciano Bastos for contributing to Global Insight.


[us_separator size=”small” show_line=”1″]
[us_image image=”9427″]
[us_separator]

Mr. Bastos is the director and clinical instructor of specialty contact lenses at the Instituto de Olhos Dr. Saul Bastos (IOSB), and is the director and specialty lens consultant of Ultralentes, a small laboratory specializing in GP and scleral lens designs in Porto Alegre, RS, Brazil.

[us_separator size=”large”]
[us_separator show_line=”1″ size=”small”]
[us_post_navigation in_same_term=”1″]
[us_sharing providers=”facebook,twitter,linkedin” align=”right”]
Tags: , ,

Maximising Oxygen in a Post PKP Patient

[us_post_title][us_post_date][us_separator size=”small”]

by Steven Sorkin, OD, FSLS

Patient History

A new patient was referred for specialty contact lens evaluation by his corneal surgeon.

The patient is a 61-year-old male who has a complex ocular past history. He has a history of ocular trauma to the right eye approximately 5 years prior. A wood-based foreign body had caused a corneal ulcer and subsequent dense corneal scarring which necessitated a full-thickness penetrating keratoplasty 6 months after the original injury. One year later he required cataract surgery in that eye. He subsequently developed a full-thickness macular hole in the previously normal left eye leaving him with 20/400 best corrected acuity in the left eye. Being monocular at this point, corneal GP lenses and hybrids were tried with poor success. He was referred to me for scleral lens evaluation.

Maximising Oxygen Post PKP

Evaluation

Entering uncorrected visual acuities were counting fingers in both eyes.

Refraction in the right eye was -6.00 +7.00 x 075 20/50. The left eye did not improve past 20/400.

Baseline pachymetry was 650 microns in the right eye.

Maximising Oxygen Post PKP

Specular microscopy was 1113 cells/mm squared with good CV and HEX values.

K’s were 42.50/52.12 M 070 in the right eye.

Goldmann tonometry was 14/15.

Anterior segment evaluation of the right eye showed a healthy full-thickness PKP. No microcystic edema, corneal staining or keratic precipitates were observed.

Retinal exam was unremarkable in the right eye with no maculopathy.

Maximising Oxygen Post PKP

Scleral Lens Fit

A detailed discussion with the patient regarding risks and benefits of contact lens wear occurred at the consult visit. After this discussion, we commenced with a diagnostic scleral lens fit. The diagnostic lens had 296 microns of clearance after 30 mins of settling. Over refraction improved his visual acuity to 20/25-.

A lens was ordered for the patient in the following parameters:

Blanchard One Fit Med

OD central vault 5050/ Rx -5.00/ M-50/L STD/ EDGE +150/+75/Diameter 15.6/ CT 0.24

I ordered the lens in Optimum Infinite material to maximise the oxygen permeability in this post graft patient.

At the dispense visit, central vault was 192 microns and overall lens fit was acceptable. Edge configuration was good without edge lift or blanching. Visual acuity was 20/25- and the patient was very pleased with comfort as well.

Follow Up Visit

At the one week follow up visit, the patient was very happy with the lens. The fitting evaluation was excellent with a final central vault of 150 microns after 6 hours of wearing time. The mid-peripheral fitting relationship was also good with no touch. No distress to the corneal transplant was noted. Central corneal thickness was noted at 665 microns, a nominal increase from baseline. No further lens adjustments were needed. The patient can wear his lens greater than 12 hours per day. A six-month evaluation also showed no change.

We are following him every three months to monitor his corneal transplant and perform sequential pachymetry, specular microscopy and topographies to watch for any adverse effects or complications going forward. For this patient, utilising a hyper Dk lens material and minimising lens thickness, along with a proper fitting lens improved the quality of vision in this monocular patient that has a challenging ocular history.

Thank you to Steven Sorkin, OD, FSLS for contributing to Global Insight.

[us_separator size=”small” show_line=”1″]
[us_image image=”9433″]

Dr. Sorkin serves as the Director of Specialty Contact Lens Services at Corneal Associates of New Jersey in Fairfield, New Jersey. He earned his Doctor of Optometry degree from the State University of New York College of Optometry. He lectures extensively throughout the United States and internationally on contact lenses, dry eyes, ocular therapeutics and corneal diseases. He has a special interest in difficult to fit contact lens patients, such as those with keratoconus and post surgical cases and manages many patients with complex anterior segment conditions. He participates in many contact lens related studies. Dr. Sorkin currently serves as President of the Essex County Optometric Society and is a  member of the Board of Directors of the New Jersey Society of Optometric Physicians.  He is also a Fellow of the Scleral Lens Education Society and is adjunct faculty at Salus University. He was named New Jersey Optometrist of the Year by NJSOP in 2018.

[us_separator size=”small” show_line=”1″]
[us_post_navigation in_same_term=”1″]
[us_sharing providers=”facebook,twitter,linkedin” align=”right”]
Tags: , ,